



Southern Lebanon under daily Israeli attacks: Disrupted services and ongoing uncertainty

Southern Lebanon under daily Israeli attacks: Disrupted services and ongoing uncertainty

Despite a fragile ceasefire, which was announced on 21 June 2026, and ongoing Israeli airstrikes in southern Lebanon, hundreds of thousands of people have decided to return to their hometowns, while others are forced to remain in displacement.

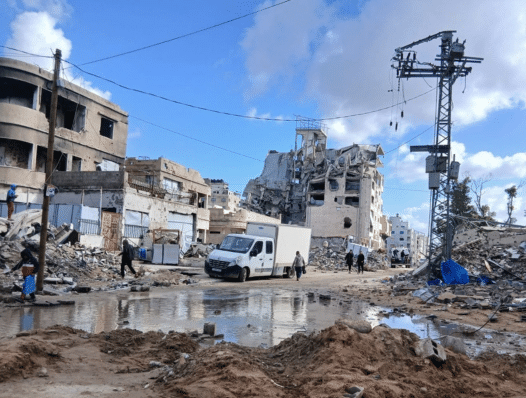
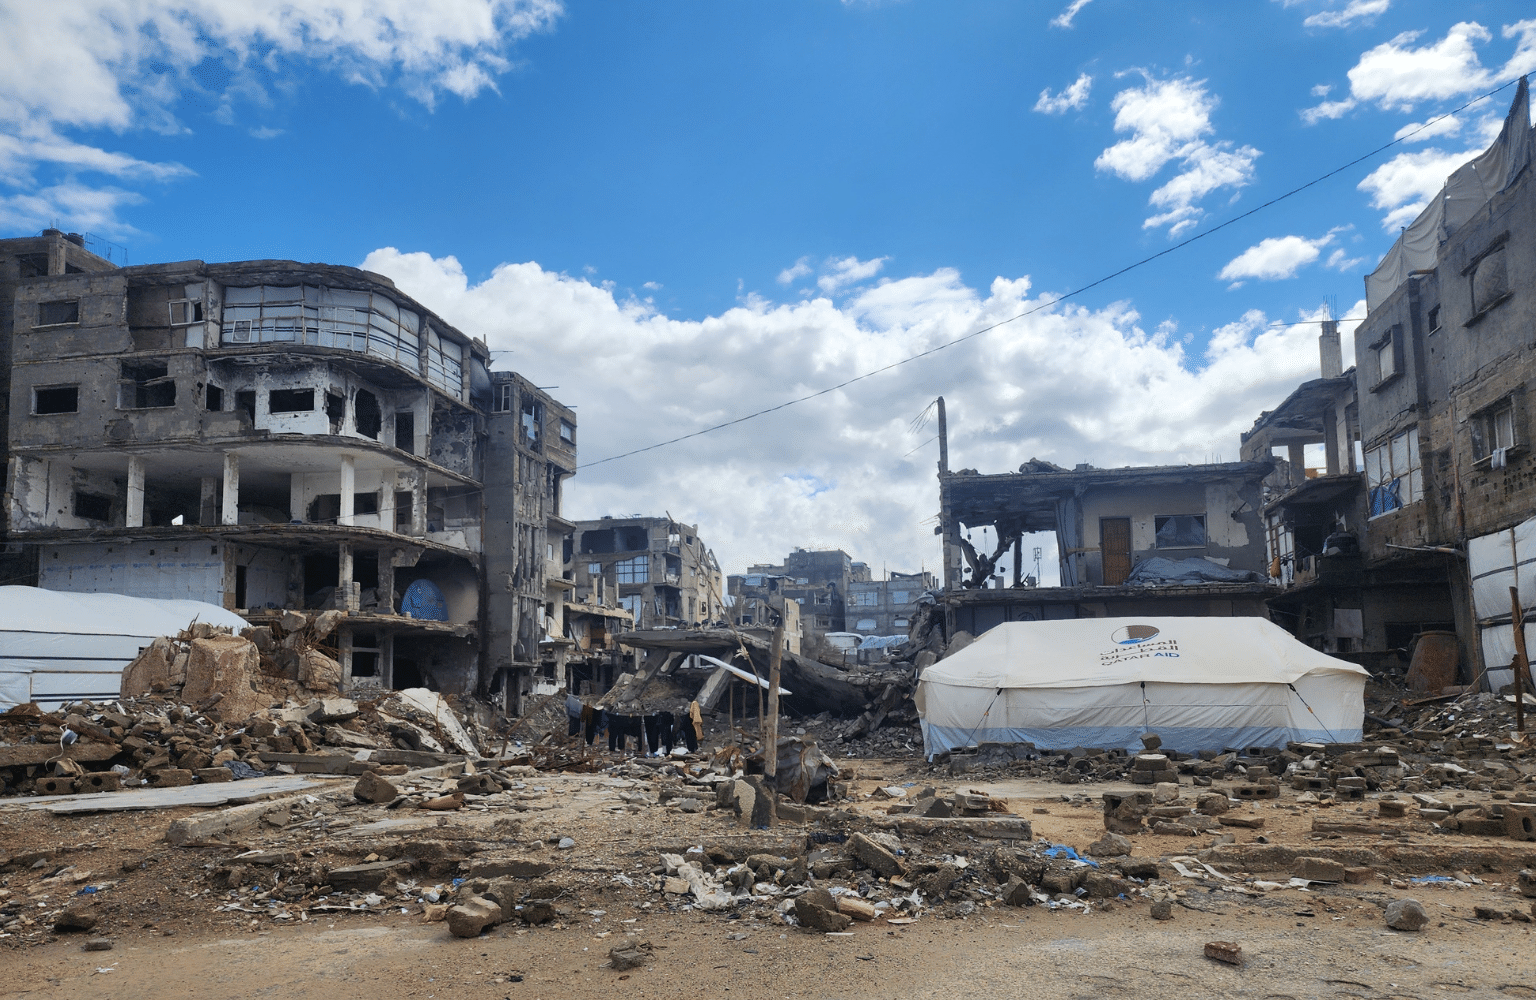
Villages along the southern border are still inaccessible because of the ongoing presence of the Israeli forces. In the villages adjacent to these, houses, roads, water networks and public services have been damaged or destroyed by Israeli attacks. Even where people can physically return, many struggle to imagine how they can rebuild their lives.

Remaining in displacement is not a choice; people have nowhere to go. With no access to basic services and nonstop Israeli attacks on their villages and towns, some people cannot return to their communities. How could they plan for tomorrow when insecurity and uncertainty shape every part of daily life?
Jean-Marc Biquet, MSF project coordinator in Lebanon

As some families try to return, they need a doctor when someone falls ill. They need clean water running from the tap. They need a roof that protects them and a sense that their children can sleep safely at night.

Without these essentials, returning home risks becoming another hardship rather than the end of one.

To help communities navigate these challenges, MSF is supporting access to healthcare, shelter and water, services that people rely on every day and that become even more critical during times of crisis.

Reinforcing healthcare

After months of Israeli attacks, many health facilities were left damaged, understaffed or struggling to provide services. For families considering a return, the absence of healthcare can be enough to keep them away.

People need to know that if a child has a fever or if a woman needs maternal care, there is somewhere they can turn.
Jean-Marc Biquet, MSF project coordinator in Lebanon

To help restore access to care, MSF has supported health facilities in southern Lebanon and Beirut’s southern suburbs/Dahiyeh through rehabilitation, operational support and capacity building.

This includes the full rehabilitation of a primary healthcare centre in Haret Hreik and ten ambulances serving communities across southern Lebanon, helping healthcare workers to continue to provide medical aid where it is needed most.

When home is no longer there

In the villages that are theoretically accessible despite daily Israeli attacks, some houses are destroyed while others remain too damaged to live in safely. Many families continue to move between temporary accommodation, relatives’ homes and collective shelters while trying to decide what the future holds.

Displacement doesn't end when the fighting stops. For many families, it continues every day they remain unable to return home or rebuild what they have lost.
Louis Dowse, MSF Country Coordinator in Lebanon.

MSF teams have rehabilitated and supported many shelters during peak of escalation and afterwards. Most recently, the team in southern Lebanon has fully rehabilitated a shelter in Jbal Al Botm for families relocated from Sour/Tyre and improved living conditions at another site in Maaroub by installing of prefabricated bathrooms and showers.

These improvements offer a temporary solution for families while longer-term solutions remain out of reach.

Restoring water, restoring daily life

Water is often one of the first services disrupted during conflict and one of the last to be fully restored.

Across southern Lebanon and Beirut’s southern suburbs /Dahiyeh, Israeli attacks have damaged infrastructure, affecting access to safe water, which adds another burden for families already coping with displacement and loss.

MSF has supported repairs to water infrastructure in several conflict-affected locations, restoring water systems, treatment facilities and solar-powered networks that communities depend on every day. The teams have also provided fuel to shelters and displacement sites to help keep water pumping and electricity systems operational.

For families trying to move forward, these simple services, which are taken for granted in many places around the world, are what make their daily life possible.

Across southern Lebanon, people are rebuilding while continuing to live with uncertainty. They are doing everything they can to move forward. What they need is a chance to rebuild their lives with dignity, even when the future remains uncertain.
Louis Dowse, MSF Country Coordinator in Lebanon.
Facebook
Twitter
LinkedIn
WhatsApp
Print

Three years on, Israel is asphyxiating Gaza and dismantling the means of survival

Three years on, Israel is asphyxiating Gaza and dismantling the means of survival

[Amman / Jerusalem, 5 October 2026] – Médecins Sans Frontières (MSF) warns that Israel is progressively asphyxiating Gaza and continuing its genocide: the space in which people can live is vanishing, while the conditions people need to survive are being systematically destroyed through continued violence, the deliberate blockade of essential supplies, and the destruction of healthcare and vital infrastructure.

In the past year, the physical trapping of people in Gaza has been made increasingly definitive by the establishment of Israel’s Yellow Line. Originally presented as a temporary, first-phase military withdrawal position and a key part of maintaining the so-called ceasefire – it is now reinforced by military positions, berms and ongoing demolitions and has continued to move west, squeezing people into a smaller and smaller area. Israeli forces now occupy approximately 65 per cent of Gaza, using the line to draw a clear border around this area.

As the Yellow Line moves, the threat to people living nearby becomes increasingly immediate, compounded by the uncertainty of approaching a line that is not clearly or consistently demarcated. People risk being shot by Israeli forces when they approach it, and MSF teams continue to treat people with gunshot wounds sustained nearby. Its encroachment is also disrupting the delivery of essential assistance: MSF water trucking has had to stop when shooting occurs near communities living close to the Yellow Line.

The Yellow Line cannot be treated simply as a line on a map. It has become a mechanism of encirclement and ethnic cleansing, while cutting communities off from the infrastructure, healthcare, water and other essentials they need to survive.
Amande Bazerolle, MSF head of emergency response in Gaza

Nor is violence confined to the areas around the Yellow Line. In June and July alone, despite a so-called ceasefire, MSF teams treated more than 1,200* cases of violent trauma across Gaza, including blast injuries, burns, gunshot wounds and injuries resulting from physical assault. Over the past three years, our teams have treated more than 200,000 trauma cases*, including injuries resulting from intentional physical violence, while Israel’s military offensive has killed more than 74,000 people, including more than 20,000 children.

As Israel confines Palestinians into increasingly limited areas, families are being pushed into overcrowded and unlivable conditions, without sufficient access to clean water, sanitation, shelter or healthcare. These conditions are contributing to the spread of disease. MSF teams have treated more than 11,000 cases of skin diseases such as scabies this year alone, while seeing more than 1,500 cases of chickenpox in June and July. MSF distributed around 2.1 million litres of drinking water per day in August, yet the scale of need remains far beyond what can be met under these restrictions.

Most people have less than six litres of domestic-use water per day and limited access to basic hygiene items such as soap and detergent. We are treating gastroenteritis, acute respiratory infections, a lot of skin conditions, hepatitis, bacterial skin infections, scabies and lice. At the same time, we are facing severe shortages in terms of medical supplies. Even the cream we need to treat scabies has been restricted by the Israeli authorities.
Dr Murad Asaliyya, medical activities manager in Gaza

Over the past three years, access to healthcare has deteriorated dramatically, with hospitals increasingly running out of basic supplies and patients unable to access essential medicines and treatment. Restrictions on essential supplies such as engine oil and spare parts are also crippling the infrastructure needed to keep hospitals, ambulances and water systems running, with generators already breaking down and water-trucking operations reduced.

The destruction of Gaza’s healthcare system, damage to more than 80 per cent of all structures in Gaza[1], alongside the lifelong physical and mental health impacts of repeated violence and displacement, will extend far beyond the present and prevent any meaningful recovery for years to come.

[1] UNDP: Clearing most of the rubble in the Gaza Strip is possible in seven years under right conditions – Question of Palestine

Nor is this crisis limited to Gaza. Since 2023, violent settler attacks, military operations and raids on homes, displacement camps and agricultural land, illegal settlement expansion, displacement, home demolitions and movement restrictions have rapidly escalated across the West Bank and East Jerusalem, particularly this year. Patients at MSF clinics tell teams about homes being demolished by Israeli forces, attacks by settlers and livestock being stolen. The policies of violence, harassment and forced displacement affecting Palestinians extend beyond Gaza, causing further fragmentation of the occupied Palestinian territory.

It will take generations to recover from the harm that has already been done over the past three years, and in the preceding decades, while the excruciating consequences of Israel's ongoing genocide are still being felt every day. Destruction, displacement and deprivation have become normalised - practices Israel is carrying out with impunity. Governments must act now to ensure Israel stops the destruction and killing, prevents ethnic cleansing, and stops denying Palestinians the means of survival.”
Amande Bazerolle, MSF head of emergency response in Gaza

* This refers to cases not patients, including new or follow up consultations.

Facebook
Twitter
LinkedIn
WhatsApp
Print

Behind the Call: Living with the psychological toll of war in Lebanon

Behind the Call: Living with the psychological toll of war in Lebanon

For people in southern Lebanon, the war has not ended with the announcement of yet another so-called ceasefire. Fear, uncertainty and daily Israeli attacks continue to endanger people and weigh heavily on their mental health.

Leaving home means losing routines, livelihoods and a sense of stability, while the possibility of having to flee again remains a constant concern. Even with the announcement of yet another so-called ceasefire, Israeli attacks and demolitions in southern Lebanon continue, and the fear of what might happen next hangs in the air, almost as persistent as the buzz of Israeli drones overhead.

“I wasn’t sure if I was affected by the war, until people around me started to notice my anger, my irritability and suggested that I should get help,” said Lara*, a 33-year-old mother from Saida. She described the challenge of dealing with her own distress while parenting, “How do I keep on working on myself while taking care of my children?”

When active shelling, destroyed infrastructure, displacement, and road hazards made travelling to physical clinics difficult, Médecins Sans Frontières/Doctors Without Borders (MSF) brought mental healthcare directly to people through a remote support service. Free tele-mental health proved that safety and psychological continuity can be a priority even when all facets of normal life come under fire.

For people who remain in areas affected by Israeli bombardment, there may be little space to process what they are experiencing while the threat itself continues.

Ali*, a 37-year-old man from Arzay, in the Tyre district, stayed in his village because his family had nowhere else to go. During a psychological support session with MSF, he said he was tired of hearing the bombing when the sound of a low-flying Israeli aircraft interrupted his train of thoughts.

“There are warcrafts. I have to hang up. I’m packing my bag.”

He ended the call to prepare to leave.

What we are seeing is that people are not only dealing with what is happening to them, but with the uncertainty of what might happen next. For people who have been displaced or remain in areas affected by attacks, there is often no real opportunity to feel safe, settle down and process what they have experienced. This has a profound impact on their mental health.
Yara Kassar, MSF mental health supervisor in southern Lebanon.

Amin*, 33, was displaced from Beirut and described his resignation during a psychological support session with MSF psychologist over the phone.

“I keep telling myself everything will be okay, but I don’t believe my own words anymore. Every night I wait for the next sound that will make us run again. I wish I could shut down my negative thinking.”

Finding support when care is difficult to reach

With the 2 March escalation, Israeli bombardment raged across Lebanon, and displacement, insecurity, damaged infrastructure, financial hardship and unsafe roads all made accessing healthcare a daily challenge. People often prioritised the immediate needs of their families over their own mental health.

In response, MSF launched an emergency response across the country. Integrated into the response was a free and confidential mental health helpline, providing remote psychological support to people experiencing distress because of the war. It complements the broader response, which includes mobile medical and mental health teams, as well as face-to-face provision of care.

Since 2 March, the helpline has received 580 calls and provided psychological support to 421 individuals, alongside social support and referrals for specialised care.

Through the helpline, we are able to provide compassionate listening and support, whether for mental health concerns, social needs, or referral to specialised services. But a phone call cannot restore a destroyed home, end displacement or make an unsafe area secure. What it can do is provide a point of contact for people trying to cope with what they are experiencing.
Yara Kassar, MSF mental health supervisor in southern Lebanon.

For those living through continued Israeli attacks and demolitions, mental health is not separate from the wider humanitarian crisis. It is a fundamental part of it. Mental health support in times of war is not optional. It is lifesaving emergency healthcare.

As needs evolve on the ground, MSF continues to adapt its response, remaining physically present through mobile clinics and hospital interventions, while also reaching people remotely through its mental health helpline. Because when the effects of war extend beyond what can be seen, care must reach people wherever they are.

*name changed to protect identity

If you are affected by the war and would like our mental health support, call MSF on 79 409 398.

Note: MSF’s mental health helpline is free and confidential. All statements featured in this video are words shared by our patients, but have been voiced by others to protect their confidentiality.

Facebook
Twitter
LinkedIn
WhatsApp
Print

Ebola in eastern DRC: An outbreak unfolding amid conflict, displacement and multiple health emergencies

Ebola in eastern DRC: An outbreak unfolding amid conflict, displacement and multiple health emergencies

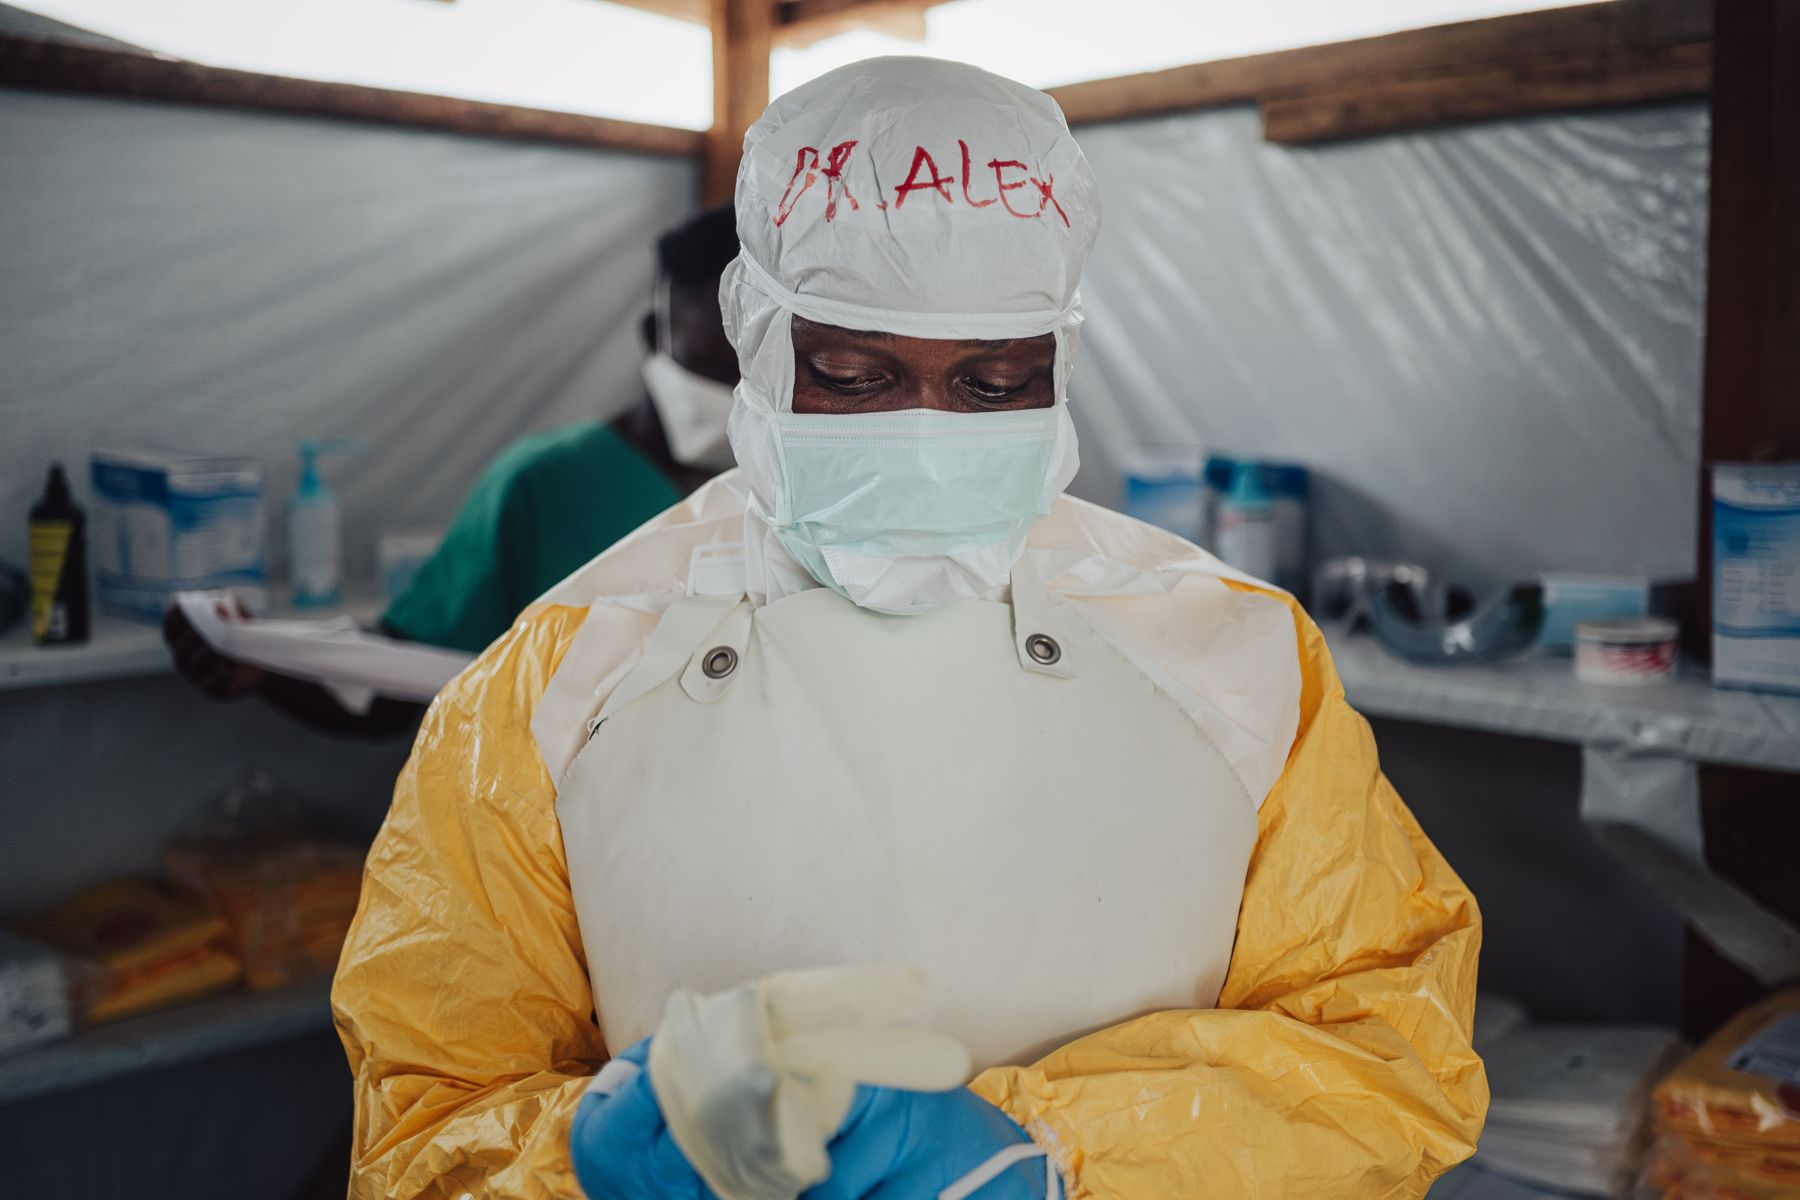
Since Ebola disease was declared in the Democratic Republic of Congo (DRC) on 15 May 2026, the outbreak has spread through a region already facing armed conflict, repeated displacement and an overstretched health system.

The timeline below traces the evolution of the outbreak and MSF’s response, while highlighting how insecurity, displacement and other health emergencies are shaping efforts to contain Ebola.

15 May 2026

An Ebola outbreak is declared in northeastern DRC

On 15 May, health authorities in DRC officially declared an outbreak of Ebola disease caused by the Bundibugyo virus.

Days earlier, MSF had received alerts of unusual deaths linked to a suspected viral haemorrhagic fever in Mongbwalu health zone, northwest of Bunia in Ituri province. An assessment with the Ministry of Health found that 55 people had died in the area since the beginning of April.

By the declaration, authorities had reported hundreds of suspected cases and more than 80 deaths across Mongbwalu, Bunia and Rwampara health zones. A case had also been confirmed in neighbouring Uganda.

MSF began preparing a large-scale response, deploying specialised teams, medical supplies and protective equipment while expanding isolation and patient-care capacity.

29 May 2026

Two weeks in, the outbreak is moving faster than the response

By 28 May, confirmed and suspected cases had been reported across Ituri, North Kivu and South Kivu. Limited testing and difficulties reaching some areas meant the full scale of transmission remained unclear.

MSF rapidly expanded activities. A 65-bed Ebola treatment centre was under construction in Ituri, while temporary isolation structures were established in Mongbwalu and Fataki. Teams also reinforced infection prevention and treatment capacity in Bunia and several locations in North Kivu.

Yet hundreds of samples were awaiting laboratory processing, and isolation and treatment capacity remained insufficient.

15 June 2026

One month on, major gaps remain

One month after the declaration, MSF warned of major gaps in surveillance, diagnosis, contact tracing and community engagement.

Treatment centres in Ituri were under intense pressure, with many patients arriving only after becoming severely ill. Testing remained particularly limited in areas affected by insecurity, while access constraints prevented response teams from reaching some communities.

Conflict changes the response

Ebola is unfolding in a region where armed conflict has disrupted healthcare for years. Fighting can make communities inaccessible, interrupt roads and services, separate families from health facilities and complicate contact tracing.

Insecurity can also slow the movement of specialised staff, protective equipment and laboratory materials. These constraints directly affect the core tools needed to contain Ebola: early detection, testing, safe referral, treatment and sustained engagement with communities.

Trust is equally important. Effective Ebola responses depend on communities understanding and participating in health measures. Community leaders, patients, families and health workers need to be involved in how cases are identified, referred and cared for.

15 July 2026

Two months into the outbreak, cases continue to rise

By the two-month mark, more than 2,000 confirmed Ebola cases and 750 deaths had been reported.

In less than five weeks, confirmed cases had approximately tripled. In Bunia, the 90-bed Elikya Ebola treatment centre was regularly operating close to capacity, and some people delayed seeking care because they feared no bed would be available.

MSF called for a broader response, including expanded testing, treatment capacity, surveillance, contact tracing, community engagement and survivor care.

July–August 2026

Displacement adds another layer of vulnerability

As Ebola continued to spread, hundreds of thousands of people in eastern DRC were already living with the consequences of repeated displacement.

Displaced families may face overcrowding, reduced access to clean water, interrupted vaccination and difficulty reaching healthcare. Repeated movement can also make surveillance and contact tracing more difficult.

At Rho displacement camp near Drodro, Ituri, where nearly 50,000 people were living, community leaders worked with MSF to encourage early testing and treatment and strengthen infection prevention.

Their involvement showed that displaced communities are not simply recipients of emergency assistance. Their knowledge, participation and trust are essential to making the response effective.

14 August 2026

Ebola is not the only health emergency

As international attention focused on Ebola, MSF warned that other urgent health needs in eastern DRC could not be neglected.

Cholera, measles and malaria continued to affect communities in North Kivu and South Kivu, alongside conflict-related injuries and the health consequences of displacement and sexual violence.

From January to 19 July, official figures recorded more than 108,000 suspected measles cases and 1,394 deaths across DRC. More than 35,000 suspected cholera cases and over 1,000 deaths had also been reported.

For people living in eastern DRC, these emergencies overlap. A family displaced by violence may simultaneously need clean water, malaria treatment, childhood vaccination, maternity care or treatment for cholera or measles.

Fear of Ebola can also discourage people from visiting health facilities for other illnesses. Routine healthcare therefore needs to continue alongside the outbreak response. Stopping Ebola cannot mean allowing other urgent health needs to go untreated.

21 August 2026

Approaching 100 days, the response must become more flexible

Nearly 100 days after the outbreak was declared, Ebola had become the largest and deadliest outbreak recorded in DRC’s history.

As of 16 August, national authorities had reported more than 5,000 confirmed cases and more than 2,400 deaths. MSF reported that more than 60 per cent of Ebola deaths had occurred outside treatment centres, often far from specialised facilities.

By August, more than 1,400 MSF staff were supporting the response across several affected provinces, operating treatment centres and isolation units while strengthening local health facilities and community-based activities.

The situation underscored the need to bring testing, isolation, referral and treatment closer to affected communities.

The emergency is Ebola—and everything surrounding it

The outbreak has exposed the pressures already affecting eastern DRC’s health system. Ebola requires rapid detection, testing, treatment, infection prevention and strong community engagement, but each becomes harder when insecurity restricts access, people are repeatedly displaced and other diseases continue to spread.

Responding to Ebola therefore requires more than containing one virus. Resources for the outbreak need to reinforce, rather than eclipse, the wider medical response.

For communities living through the crisis, there is no neat separation between Ebola, cholera, measles, malaria, maternity needs or injuries caused by conflict. Each requires timely access to care.

The Ebola outbreak and the response are ongoing.
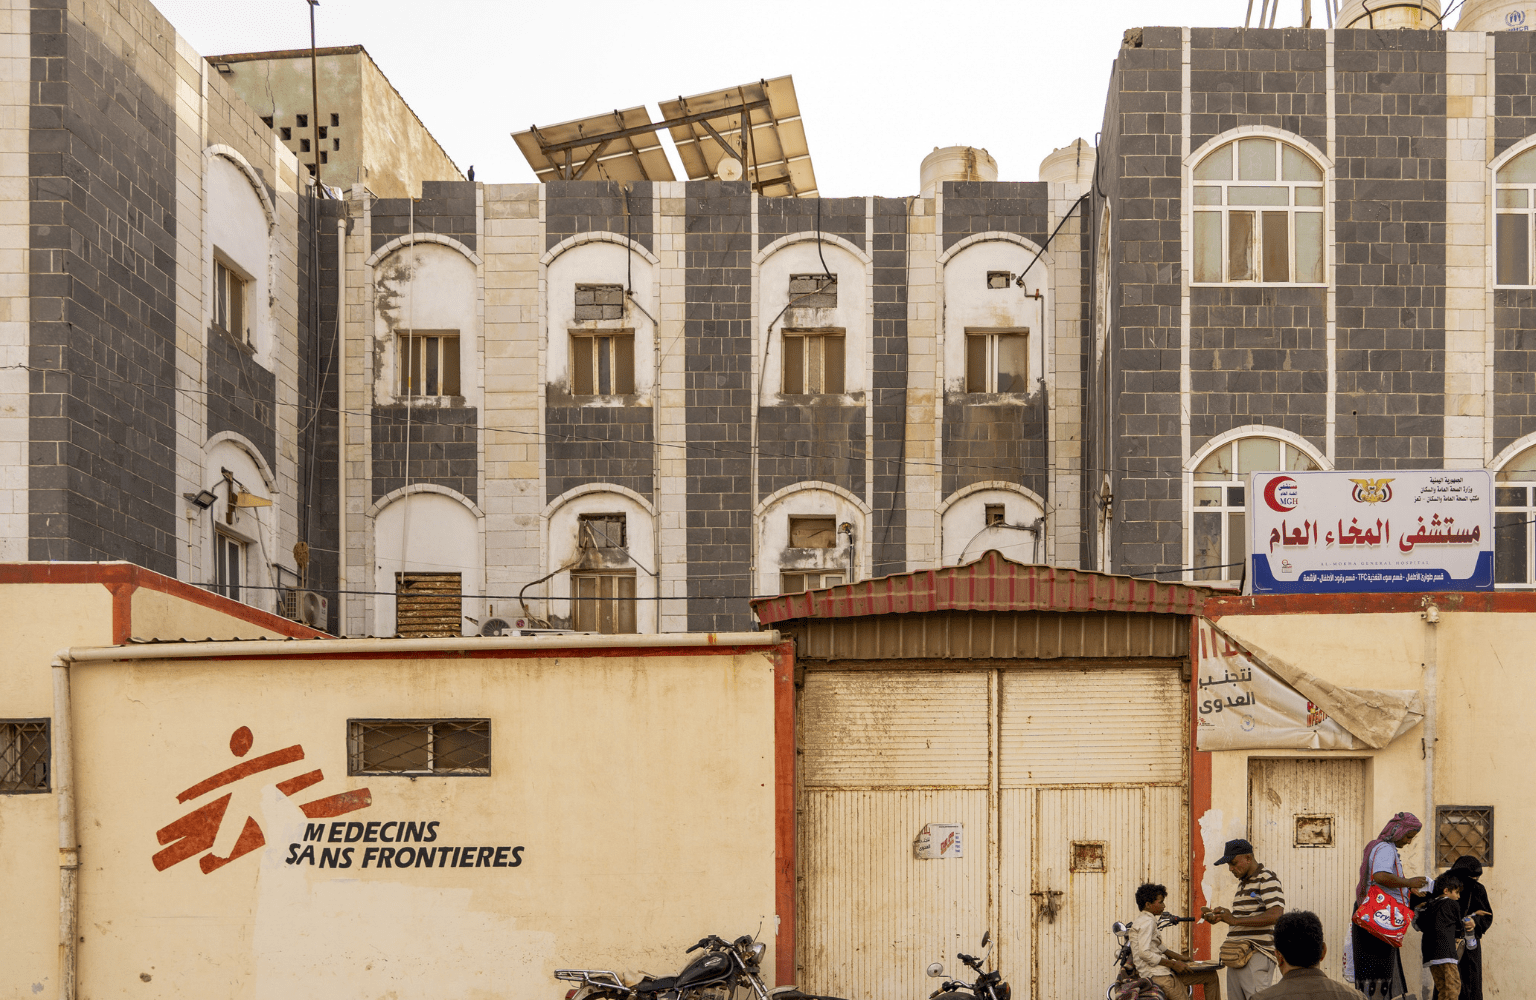
A Lifeline for Women and Children in Mocha, Yemen

A Lifeline for Women and Children in Mocha, Yemen

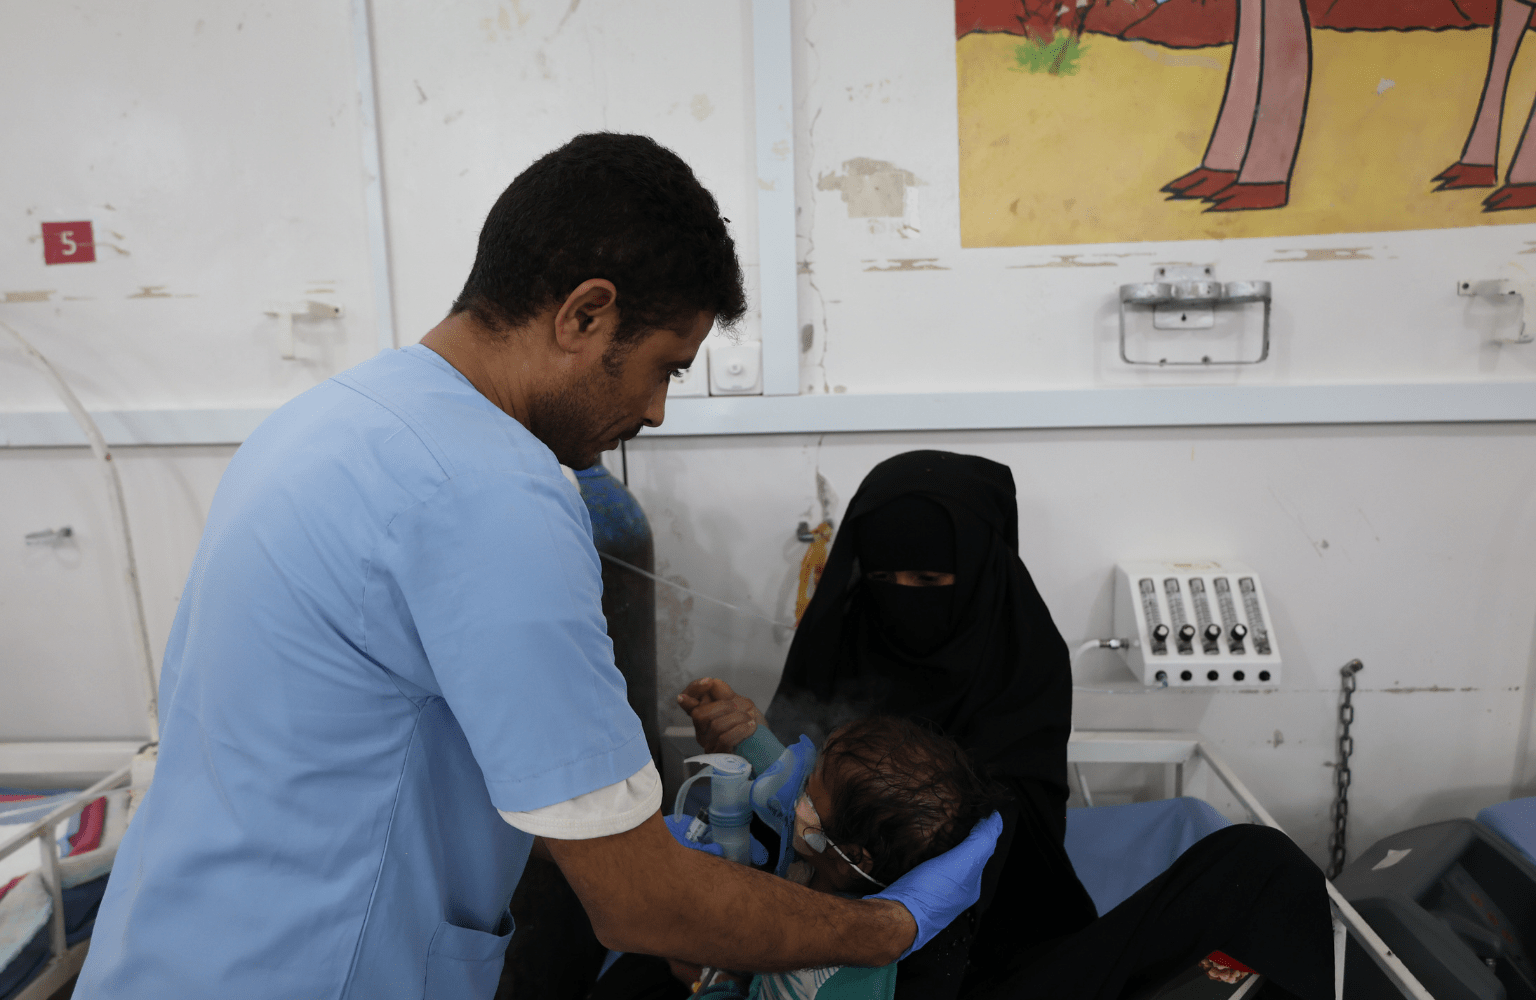
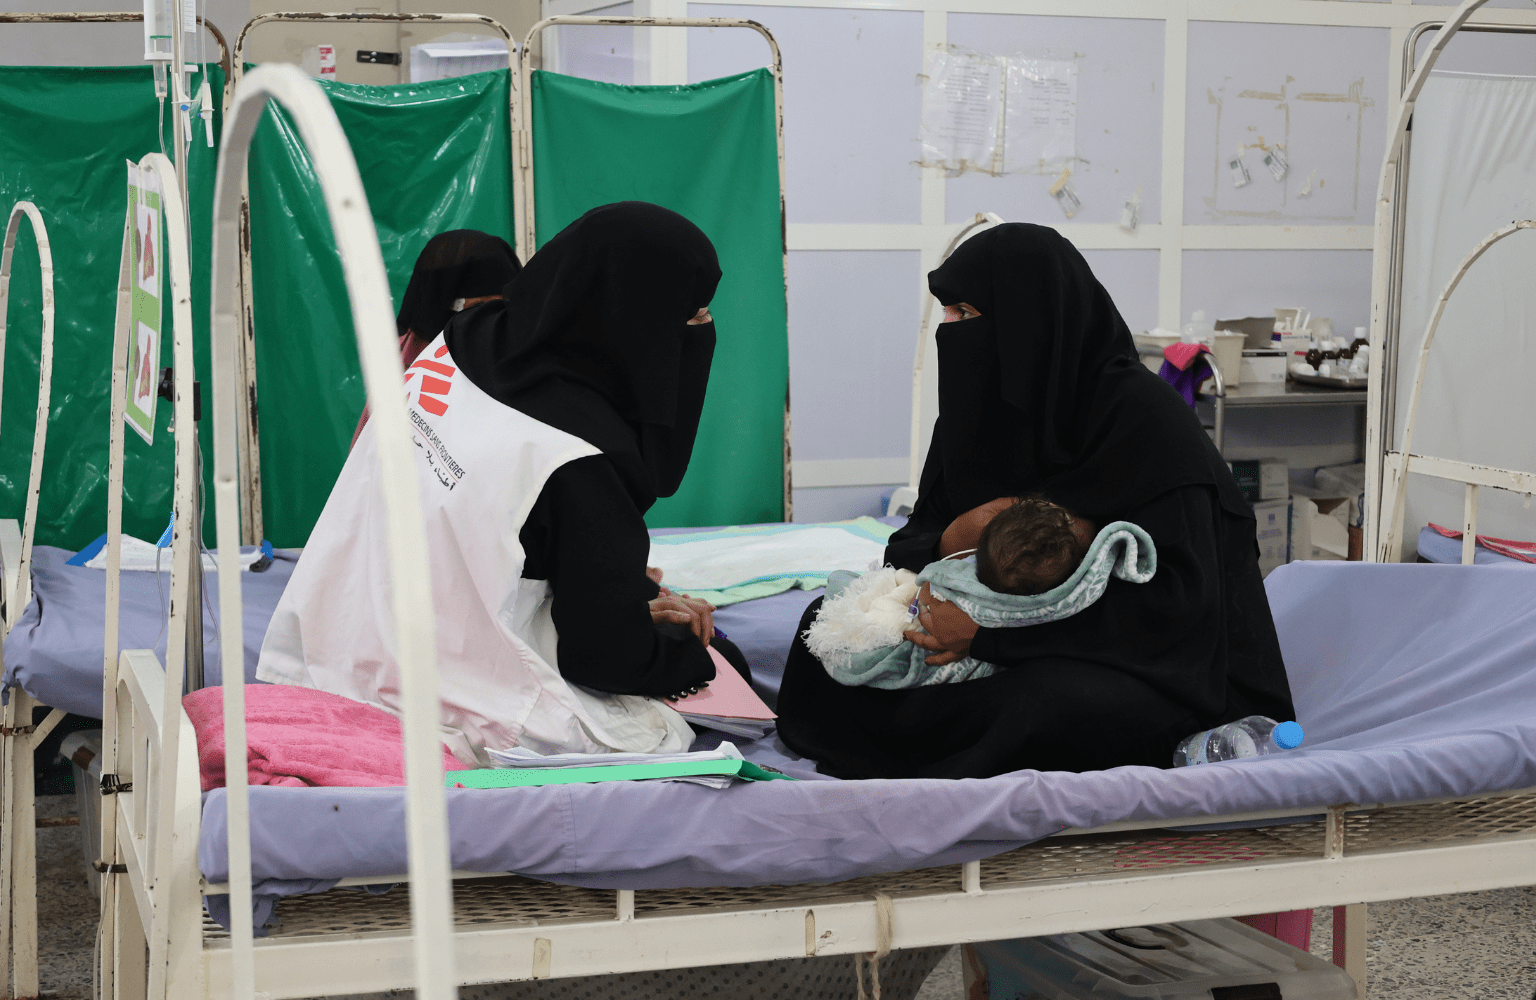
In western Yemen, Mocha General Hospital is one of the few health facilities still providing essential medical care to women and children following the recent escalation in the conflict. Sara Ahmed, Health Promotion Supervisor for Médecins Sans Frontières (MSF) in Mocha, describes the growing needs and the immense challenges faced by patients and medical teams.

In a voice message shared on 16 September, Sara explains how Mocha General Hospital has become a lifeline in a city where access to medical care has become increasingly difficult.

“We have had to scale back some of our activities and focus on the most essential services. The [health workers] remaining at the hospital are (…) working under very difficult circumstances and doing everything they can to keep the services running.”

MSF has been providing medical and humanitarian assistance in the region of Mocha since 2018, with a particular focus on the city of Mocha, Mafraq and Al Khawkha.

Our work has centered mainly on maternal and child healthcare, as well as referring patients who require more advanced or specialised care. [But we] have had to scale back some of our activities (…). We are doing everything we can to keep essential medical services running at Mocha General Hospital, particularly for women and children.
Sara Ahmed, MSF Health Promotion Supervisor in Mocha

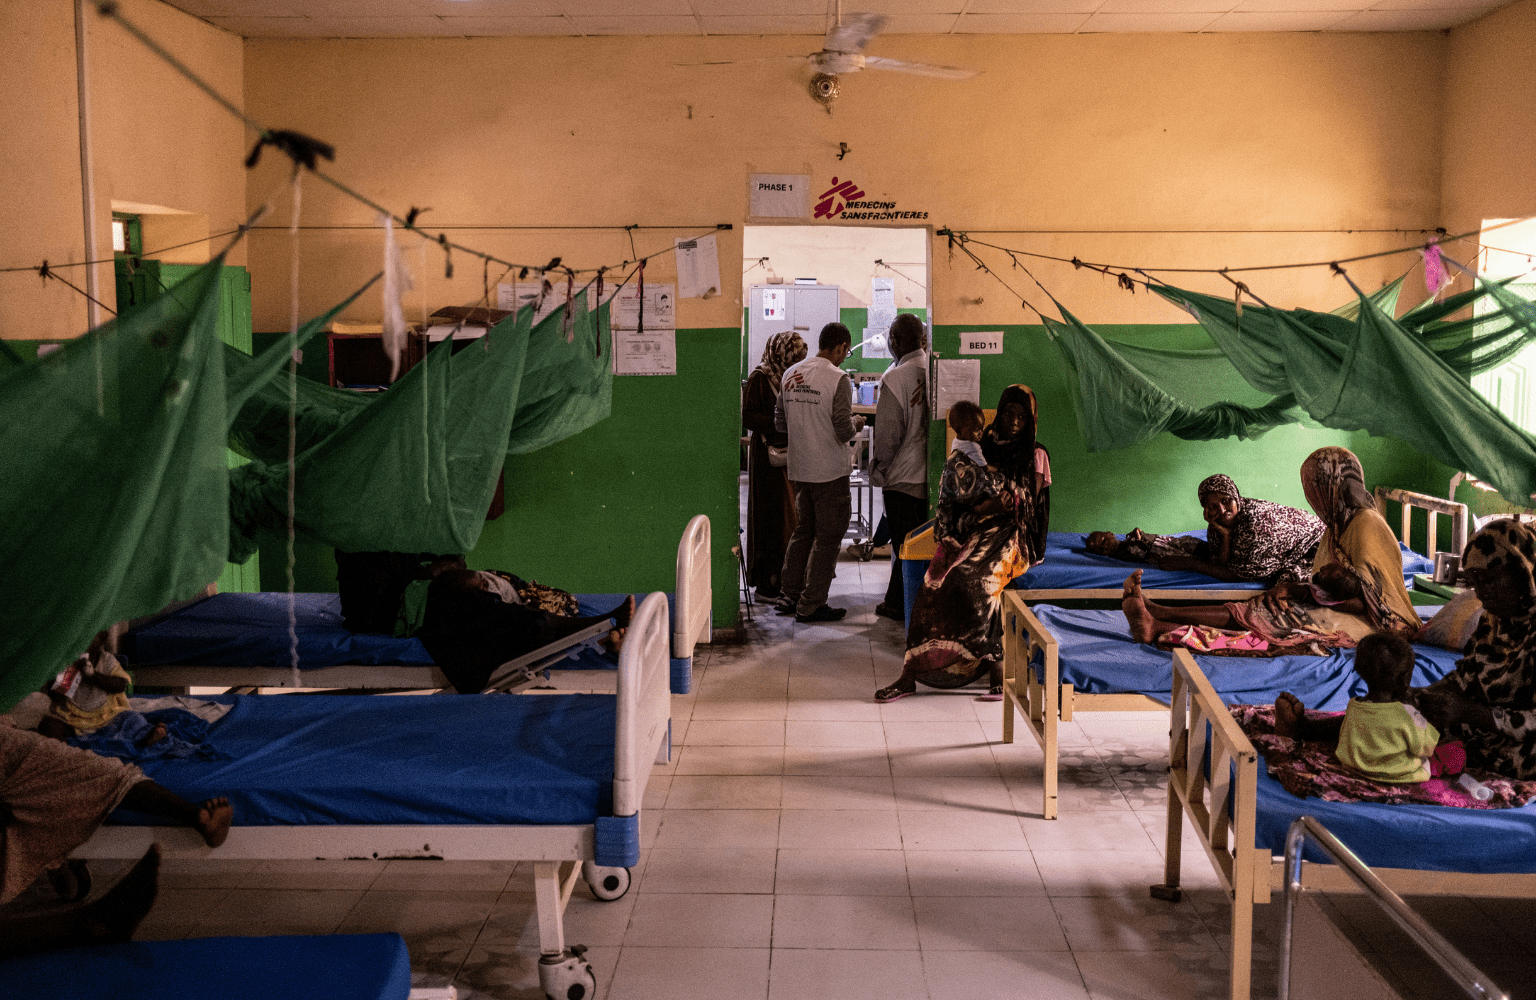
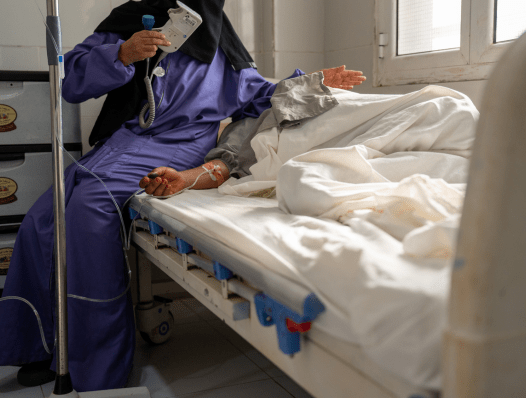
With most of Mocha’s other health facilities currently unable to operate due to a lack of personnel, the General Hospital has become a critical lifeline for people in need of medical care. As of 14 September, 30 patients were receiving treatment at the hospital, including babies in the neonatal intensive care unit and four women who were giving birth.

“The needs are extremely high and (…) it’s not just about people injured as a result of the violence: there are pregnant women who need urgent care, women who need caesarean sections, children who need treatment, and patients with illnesses that simply cannot wait.”

Last night we heard airstrikes, which obviously heighten the fear and pressure felt by both the local population and our teams. We are here to provide medical assistance. And as long as we can do so safely, we will continue to do everything we can to support those who still need it.
Sara Ahmed, MSF Health Promotion Supervisor in Mocha

At the end of the day, this isn’t just about MSF or our teams. It’s about a pregnant woman who needs an emergency caesarean section. It’s about a sick child who needs treatment.”

In addition to Mocha, MSF teams are responding to the direct impact of the current situation in other parts of the country. They are supporting hospitals in Aden, Hodeidah, Abs, Taiz, Al-Bayda and Al-Jawf by strengthening their triage capacity and providing them with essential medicines, medical supplies and trauma kits.

Facebook
Twitter
LinkedIn
WhatsApp
Print

Strengthening Healthcare Access in Daraa, Syria

A view of surroundings from the MSF supported Nawa city in Daraa governorate, southern Syria.

Strengthening Healthcare Access in Daraa, Syria

Years of conflict have severely weakened healthcare services across Daraa governorate, Syria. Health facilities continue to face shortages of trained staff, medicines, and medical supplies, alongside unreliable infrastructure and a weak referral system. Financial barriers also remain significant, with many patients having to pay out of pocket for services or medicines they cannot afford. These gaps are particularly acute for maternal and newborn care, while mental health services and treatment for chronic diseases also remain limited.

MSF Deputy Project Medical Referent accompanies a Directorate of Health nurse during a round in the MSF-supported maternity department at the Nawa National Ho

In the Nawa region of Daraa governorate, the Directorate of Health estimates that around 90,500 people rely on health services in the area, including nearly 23,000 women of reproductive age and almost 18,000 children under 5. At the same time, people returning after years of displacement are adding to the demand on already strained services. Nawa National Hospital serves communities from across the surrounding area and functions as an important referral facility for patients requiring secondary care.

In 2026, around 604,000 people in Daraa governate are estimated to need health assistance. As of 3 September, UNHCR recorded 149,682 refugee returnees to Daraa governorate. Nawa National Hospital serves communities across Daraa governorate and neighbouring Quneitra; MSF has previously estimated that its activities at Nawa National Hospital help support a population of around 1.2 million people across Daraa and surrounding communities.

For one family from Tal Shihab in southern Syria, reaching the healthcare they needed meant travelling to Nawa National Hospital. “Because of our difficult financial situation, I could not afford the cost of a caesarean section [for my wife],” says Bilal Bashndi, whose baby was born at Nawa National Hospital. “We came from Tal Shihab. It took us around an hour and a half by car to reach the hospital.”

Since Médecins Sans Frontières/Doctors Without Borders (MSF) began supporting Nawa National Hospital, working with the Directorate of Health to strengthen both medical services and the hospital systems needed to provide them, activities have included rehabilitation and reorganisation of key hospital spaces, repairing the hospital elevator, medical equipment, and supplies, and support to the obstetrics and gynaecology and neonatal departments.

This year, work has also included the reorganisation of the operating theatre and continued improvements to the pharmacy and other hospital support services. MSF also supports infection prevention and control, including cleaning, disinfection, and sterilisation, as well as essential services such as laundry and central sterilisation and the operation of a kitchen providing meals for patients.

At Nawa, MSF supports obstetric and gynaecological care and neonatal services, including vaginal and caesarean deliveries, antenatal and postnatal care, family planning, and care for newborns. MSF provides training for medical staff as well.

Some services have changed significantly over the past year. The neonatal department, which was previously not functioning, is now operational, while specialist coverage and access to medicines and medical supplies have improved. We can see a noticeable improvement in the services.
Tariq Al-Mohammad, MSF's deputy project medical referent

During the first year of activities, Nawa National Hospital’s obstetrics and gynaecology departments admitted more than 7,100 mothers and have assisted 3,140 births — with 794 surgical intervention — while 315 newborns were admitted  and treated with MSF-supported neonatal care.

Beyond Nawa National Hospital, MSF also supports primary healthcare services at Tasil Health Centre, helping people in Tasil and surrounding communities access care closer to where they live. Mental health, health promotion, and community engagement activities are also part of MSF’s support in Tasil.

A Directorate of Health nurse cares for a newborn in the neonatal unit at Nawa National Hospital, where MSF supports neonatal services.

Mental health needs after years of conflict

The consequences of years of conflict in Daraa extend beyond physical healthcare. Repeated exposure to violence, displacement, economic hardship, and major changes in people’s living conditions have created significant mental health and psychosocial needs. For people returning after years away, reintegrating into communities that have themselves changed can bring additional social, economic, and psychological challenges.

MSF provides mental health and psychosocial support in Nawa and Tasil, including community-based activities, individual and family support, and specialised care.

The community today needs mental health services. People have lived through years of war and repeated traumatic events.
Yousef Hannou MSF's mental health activity manager in Daraa

Hannou says that some returnees are coming back after spending many years outside Syria, sometimes to communities with damaged infrastructure, limited services, and very different living conditions from those they left behind. Adapting to these changes, alongside economic difficulties and the effects of past traumatic experiences, can further affect people’s mental wellbeing.

MSF health promotion and community engagement teams work with people in Nawa, Tasil, and surrounding communities through health education sessions, regular meetings with community representatives, and group discussions. The teams gather feedback on barriers to healthcare, concerns about the services provided, and suggestions for how they can be improved.

One of our main achievements in community engagement has been establishing networks of community health workers in Nawa and Tasil, made up of people from the communities themselves. We wanted community health workers to come from the same communities, so that participation is more effective.
Mohammad Abazid, MSF health promotion supervisor
A Directorate of Health nurse cares for a newborn in the neonatal unit at Nawa National Hospital, where MSF supports neonatal services. (2)

MSF has also strengthened infection prevention and control measures within the facility. In addition, water and sanitation teams have ensured adequate water supply and proper waste disposal at the facility over the past year. MSF is initially supporting the hospital’s water supply with around 70.000 liters of water per month. These interventions have significantly improved the overall functionality and quality of services at the hospital.

Despite incipient recovery over the past year, significant gaps remain across Daraa’s healthcare system. Substantial support is still needed to ensure patients can access consistent, good-quality care closer to home.

Facebook
Twitter
LinkedIn
WhatsApp
Print

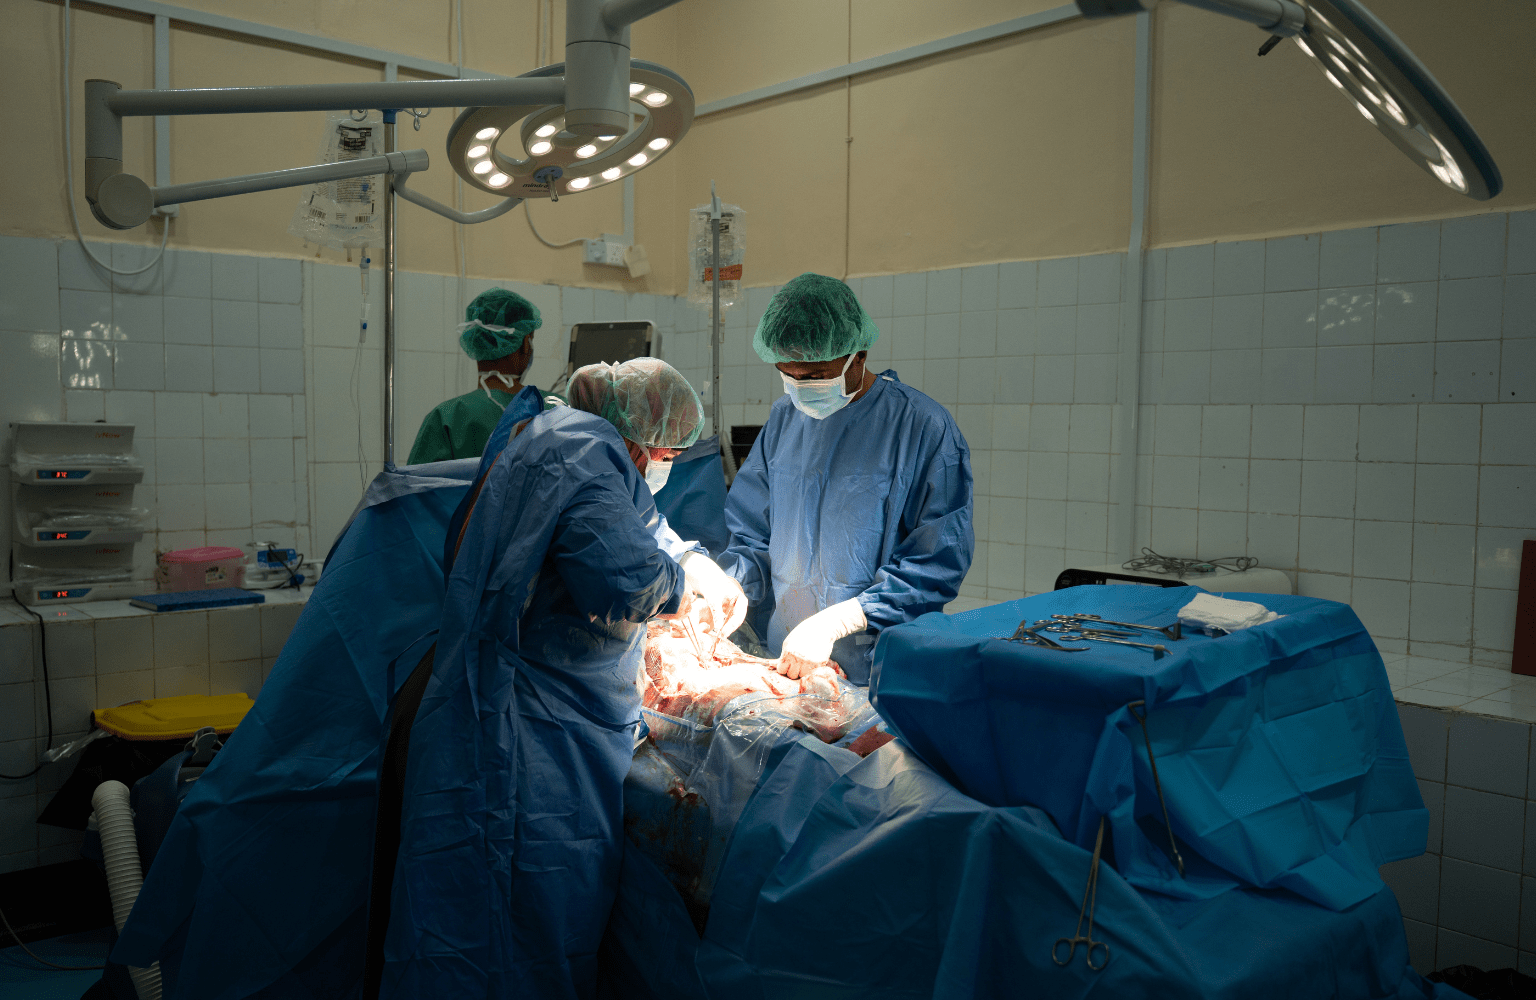
As conflict engulfs Mocha, health workers keep hospital open

Negah Abdallah Ali, 35, starting her breastfeeding journey with her newborn son Ashraf in hte recover room in Mocha Maternity in Yemen

As conflict engulfs Mocha, health workers keep hospital open

In Yemen, the escalation of the conflict and the rapid advance of Ansar Allah forces on the western coast have had a profound impact on Médecins Sans Frontières (MSF) activities. From Aden, Lou Cormack, MSF Country Coordinator in Yemen, explains the situation.

Our teams have been present in Mocha and the surrounding area since 2018. Our work focuses on improving access to paediatric and maternal healthcare, a lifeline for many women and children in an area where access to such care is a daily challenge.
Lou Cormack, MSF Country Coordinator in Yemen

In Mocha, we support the General hospital through the direct presence of MSF teams, as well as through broader support to the hospital and Ministry of Health staff. Outside the city, we also support maternal and paediatric healthcare in two healthcare centres in the region: Mafraq, east of Mocha, and Khawkhah, to the north. In these two facilities, our support includes funding, training, medical equipment, and supplies. We do not have permanent MSF teams based there.

Mocha maternity in Yemen

The rapid evolution of the situation this week, including the swift advance of Ansar Allah forces and their control of most of the western coast, has had a major impact on both medical activities and the needs of people in recent days.

Just a few days ago, our teams in Mocha were preparing to reopen our former field hospital in the city to treat patients, including providing trauma stabilisation, in response to the fighting taking place east of Mafraq and the gradual arrival of displaced people in Mocha.

The rapid advance of Ansar Allah forces has fundamentally changed the situation. Within hours, the hospitals providing trauma services on the western coast were evacuated, while large numbers of people fled Mocha.
Lou Cormack, MSF Country Coordinator in Yemen

We had already started providing water to displaced people arriving in the city, as well as finalising the setup of cholera isolation and treatment units in Khawkhah and Mocha. We were also increasing our ambulance fleet to refer critical patients to Aden, as hospitals there were at capacity.

View of the city of Mocha as seen from the maternity. The city is partly destroyed due to erosion and years of war

The rapid advance of Ansar Allah forces has fundamentally changed the situation. Within hours, the hospitals providing trauma services on the western coast were evacuated, while large numbers of people fled Mocha towards the south and Aden, including healthcare workers from the city’s hospitals. The General hospital in Mocha was no exception.

Our team remained in Mocha, but we had to scale back and reorganise our activities and focus on one immediate priority: doing everything possible to keep essential medical services at the General hospital running.

So far, thanks to the commitment of Yemeni doctors, gynaecologists, nurses, and other healthcare workers, we have been able to maintain a minimum level of essential care, including deliveries, emergency care, and intensive care. As of today, around 30 healthcare workers remain present at the hospital. This may not seem like many, but their work is saving lives.

Our medical and humanitarian mission must be respected... Without these basic guarantees, we simply cannot do our job: treating people and saving lives.
Lou Cormack, MSF Country Coordinator in Yemen

When the city was taken, dozens of patients were still hospitalised in the maternity and paediatric wards. It was essential to maintain their care while continuing to receive patients requiring urgent treatment. On that day [Thursday 10 September], hospital teams cared for two patients who arrived in the paediatric and maternity emergency departments, performed two emergency caesarean sections, and continued caring for seven patients in intensive care and 10 babies in the neonatal intensive care unit, in addition to dozens of other patients and babies in the regular wards.

The situation remains extremely challenging. As of 11 September, almost all other healthcare facilities in the city had stopped functioning, largely because their staff had left. There is currently no possibility of referring patients, either within the city or to Aden.

The medical needs were already enormous before the latest escalation. They are even greater now.

We are looking for ways to reinforce our team in Mocha, but this is not straightforward. The situation remains highly stressful for both people and our teams. There were further bombardments overnight, and there is still considerable uncertainty about what may happen in the coming hours and days.

For us to continue providing care, our medical and humanitarian mission must be respected. Medical facilities, vehicles and staff must be protected so that people can safely access the care they need. This is also essential to allow patients in critical condition to be referred safely when the treatment they need is not available locally. Any threat to the medical mission puts the provision of essential healthcare at risk and may jeopardise our ability to continue working in Mocha. Without these basic guarantees, we simply cannot do our job: treating people and saving lives.

We do not know what will happen next. What we do know is that medical needs are enormous and go far beyond trauma care. We will continue to do our utmost to support the community and maintain access to essential healthcare for as long as we can.”

Women standing in Mocha maernity in Yemen

Following the recent escalation of fighting in western Yemen, Médecins Sans Frontières/Doctors Without Borders (MSF) confirms that its teams remain in Mocha, supporting the General Hospital.

Over the past few days, many people have fled the city, including health staff from most hospitals. With several health facilities currently not functioning, the staff who remain at the General Hospital are a vital source of medical care for people in Mocha.

The needs are high and go far beyond trauma care. As of today, around 30 MSF healthcare workers are doing their utmost to help keep essential services running in the hospital, including maternity and paediatric care, as well as treatment for a range of other medical needs, including cholera.  Their work is saving lives. 

For this work to continue, the medical and humanitarian mission must be respected. Medical facilities, vehicles and staff must be protected so that people can safely access the care they need. This is also essential to ensure that patients in critical condition can be safely referred when the treatment they need is not available locally.

We are looking for ways to reinforce our team in Mocha, but this is not straightforward. The situation remains highly uncertain and is stressful for both the population and our teams. We are closely monitoring developments and engaging with the relevant authorities on the need to protect medical and humanitarian activities.

MSF has been supporting the provision of care in Mocha since 2018. Today, as yesterday, our focus remains clear: to ensure that people in Mocha can continue to access essential medical care despite the current uncertainty.

Facebook
Twitter
LinkedIn
WhatsApp
Print

Sudan Aid Cuts Force Widespread Clinic Closures

Sudan Aid Cuts Force Widespread Clinic Closures

Amidst a brutal ongoing war and a catastrophic humanitarian crisis, people in Sudan face reduced access to healthcare as facilities across the country close their doors. The impact of broad and historic international aid funding cuts by governments has begun to take hold. Médecins Sans Frontières (MSF) warns that this withdrawal of support from an already chronically underfunded crisis is cutting off lifesaving care and pushing the few remaining hospitals to breaking point.

As world leaders gather at the UN General Assembly, governments and institutional donors must protect funding for essential health services in Sudan and provide flexible transitional financing where facilities are at risk of closure.

With aid organisations pulling out, local clinics are left without the funds or medicines needed to function. For patients, this means enduring long, dangerous journeys just to receive treatment. As they seek help wherever they can, the few hospitals still operational are absorbing the overflow: between January and April 2026, admissions in MSF supported facilities in Zalingei and Rokero, in Central Darfur state, jumped by 22.5 per cent compared to the same time last year. The situation has deteriorated even further as in May alone 45 general healthcare centres in Central Darfur stopped receiving support as the organisation that had been providing resources lacked funding.

“War is driving Sudan’s needs; funding cuts are shrinking the response,” says Muhammad Ibrahim, MSF head of mission in Sudan. “MSF’s work in Sudan is privately funded. But when funding disappears from other health services, clinics close, patients have fewer places to go, and pressure shifts to the facilities that remain, including ours.”

But when funding disappears from other health services, clinics close, patients have fewer places to go, and pressure shifts to the facilities that remain, including ours.
Muhammad Ibrahim, MSF head of mission in Sudan

“Donors must protect essential health services and provide sustained, flexible funding to organisations that depend on it,” says Ibrahim.

In Tanedba camp, in Gedaref state, home to 18,400 refugees, the sudden departure of a humanitarian organisation in June resulted in the camp’s maternity and surgical wards closing. Pregnant women who need caesarean sections now face three-hour journeys to the nearest city. MSF has stepped in to run the emergency room there through the end of 2026.

In 2021, around 35 aid organisations were working in and around Um Rakuba camp in Al-Gedaref state. Today, fewer than 10 remain. The camp now hosts around 17,000 refugees, mostly women and children.

“Our hospital in Um Rakuba is now the only lifeline left for both refugees and the local Sudanese community,” says Fabrizio Locuratolo, MSF humanitarian affairs manager. “But the cuts here go well beyond healthcare. Food rations are shrinking and protection programmes are being dismantled, pulling away the last safety nets and leaving refugees completely exposed.”

After the United States (US) government announced the closure of USAID (United States Agency for International Development)  in 2025, the grants to many organisations funded to work in Sudan ended in June this year. Although the US government continues to be the largest donor to Sudan, providing funding to the UN Office for the Coordination of Humanitarian Affairs (OCHA) and other organisations, many of the existing healthcare providers have been unable to find alternative funding to continue providing services, with health facilities closing in Sudan as a result.

Just as health providers faced the impending removal of US support, many European governments also reduced their assistance to people in Sudan. European and multilateral aid budgets are also shrinking globally. OECD (Organisation for Economic Co-operation and Development) preliminary data show that aid from EU institutions fell by 13.8 per cent in 2025, while several major European donors also reduced their overall aid spending.

Globally, humanitarian aid fell by 35.8 per cent. These figures do not represent equivalent cuts to Sudan, where some European donors have maintained or increased their support. But they point to a sharply contracting international funding environment. In Sudan, that wider squeeze is compounding an already severe health crisis, as specific funding withdrawals and programme closures reduce access to healthcare.

“Closing a clinic does not remove a single patient. It just sends them to the next facility,” says Sebastián Traficante, MSF emergency coordinator in Darfur. “After a longer and more expensive journey, patients often arrive in a much more serious condition, and the hospital may already be full. MSF can reinforce some services, but we cannot absorb every closure.”

In Central Darfur’s Hamidiya displacement camp, a health centre that previously provided maternity, paediatric, and mental health care is now operating at sharply reduced capacity after an international aid organisation ended its support. Daily patient visits have dropped from 200 to barely 40, and vaccinations have stopped. The fall was not a sign that people had become healthier. They had stopped making the journey to a centre that could no longer treat them. A labourer in Darfur earns roughly US$1, a day. The US$2 transport fare to reach a working clinic therefore costs about two days’ wages, leaving residents to choose between healthcare and food. 

“That money could buy food instead,” a patient told MSF. “If there is no food, there can be no health.”

Despite the presence of around 50 NGOs in Tawila, critical gaps persist for up to 600,000 displaced people. MSF runs the only 200-bed hospital in the area and is the only organisation capable of mounting a large-scale epidemic response. Malaria and malnutrition cases are already rising despite limited rainfall, ahead of the peak of the rainy season — and we expect numbers to increase as the rain intensifies. In August, our teams admitted 191 children under five with severe malnutrition to our inpatient feeding centre, and nearly 22 per cent also tested positive for malaria.  

These closures are happening during a large-scale, severely underfunded humanitarian crisis. The UN reports that 825,000 children under five are expected to suffer severe acute malnutrition and 19.5 million people faced crisis-level hunger earlier this year, meaning families either do not have enough food to eat or can only meet basic food needs by resorting to measures such as selling the assets they depend on to survive. Yet the UN’s $2.87 billion response plan is barely 41 per cent funded, and 37 per cent of Sudan’s health facilities are estimated to be completely out of service (According to the World Health Organization).

Facebook
Twitter
LinkedIn
WhatsApp
Print

Malnourished children are reaching hospitals in critical condition in Yemen

Malnourished children are reaching hospitals in critical condition in Yemen

As health and malnutrition services scale back across northern Yemen, MSF teams are treating more malnourished children with severe complications and urges donors to sustain essential support.

After more than a decade of conflict and economic decline, children across Yemen continue to face alarming levels of malnutrition. At the same time, sweeping humanitarian funding cuts have forced organisations providing health and malnutrition services to scale back or halt activities, particularly in northern Yemen. As families are pushed to travel longer distances to seek care, MSF teams are seeing more malnourished children arriving at our health with serious medical complications such as measles.

MSF calls on donors and humanitarian actors to sustain support for essential malnutrition and child health services and to ensure treatment remains accessible close to communities.

Yemen’s humanitarian response has faced chronic underfunding in recent years, further worsened by major reductions in international aid since 2025, including cuts to US-funded assistance and reductions from other donors.

In parts of Hajjah and Al Hudaydah governorates, where MSF teams work, some providers have halted activities or reduced services, leaving health facilities understaffed or without adequate supplies, limiting access to timely treatment for malnourished children.

When common illnesses become life-threatening

“Since birth, Yara has suffered from recurrent infections and fever,” says One-year-old Yara Ali’s mother, who lives in Aslam District, Hajjah Governorate. “We initially treated her with traditional remedies, including cauterisation.”

When Yara’s condition worsened, her mother brought her to Abs General Hospital where MSF supports medical services. It was not their first visit. “I brought her to the hospital once during Ramadan, once in March, and twice in April. This is her sixth visit to the hospital,” says Yara’s mother.

For Yara, recurrent lung infections are accompanied by fever, vomiting, and difficulty breathing and eating or breastfeeding.

“Every time I bring Yara to Abs Hospital, she receives the care she requires and recovers,” says Yara’s mother. “We always return home with her condition greatly improved.”

But reaching appropriate care is becoming increasingly difficult for many Yemeni families.

Fewer services, longer journeys

Even before funding cuts, families in rural areas already faced significant barriers to reaching health care. Long distances, poor roads, and transportation costs made it difficult to reach health facilities. But as health and malnutrition programmes close or reduce activities due to funding shortages, health care becomes even less accessible and the challenges of reaching it become even greater.

At the MSF-supported Al-Salam Hospital in Khamer, one mother said she travelled for eight hours with her 3-month-old baby after being unable to access the treatment the child needed in Al Jawf, closer to their home.

“My baby had diarrhoea and vomited for four days and was about to pass away,” she says. “A doctor in Al Jawf advised me to come to Al-Salam Hospital because they provide free medical services. My husband works far away from home and there was no one to take us here. We travelled from Al Jawf to Sana’a and then to Khamer, and it took us eight hours to reach the hospital.”

By the time some children reach medical care, they have developed serious medical complications. Delays in accessing treatment can turn manageable conditions into medical emergencies. MSF is witnessing this more frequently in the facilities it supports.

“I feared I would lose my daughter,” she says. “Watching her condition worsen while help was so far away was heartbreaking. Every hour felt like a race against time.”

More children arriving in critical condition

Between January and June 2026, MSF teams at Al-Salam Hospital admitted 1,296 children with severe acute malnutrition and medical complications, compared with 798 during the same period in 2025 — a 62 per cent increase.

During this same period, the hospital’s ambulatory therapeutic feeding centres treated 1,775 children with malnutrition, including 1,251 with severe acute malnutrition, and 524 with moderate acute malnutrition.

Malnutrition admissions usually rise in April before Yemen’s agricultural lean season. But the sharper increase observed this year suggests that seasonal pressures are being compounded by deteriorating living conditions and reduced access to health care.

MSF teams are seeing similar warning signs elsewhere.

At Abs General Hospital in Hajjah Governorate, MSF teams treated 1,245 malnourished children between January and June 2026. Many arrived with medical complications.

Admissions related to maternal malnutrition increased from 689 cases in 2025 to more than 1,260 cases in the first six months of 2026. This sharp increase highlights a growing burden of maternal malnutrition, placing both mothers and newborns at greater risk of adverse outcomes, including preterm birth. 

At MSF-supported facilities in Mocha, Taiz governorate (Mocha Hospital and Al-Mafraq PHC), and in Hudaydah governorate (Al-Khawkhah PHC), 4,909 children were diagnosed with acute malnutrition between January and June 2026, including 1,637 with severe acute malnutrition and 3,236 with moderate acute malnutrition.

In Al Hudaydah governorate, on the west coast of Yemen, MSF teams witnessed a sharp rise in admissions for complicated severe acute malnutrition. In just six months, MSF teams have already treated more than 50 percent of the total severe acute malnutrition cases we saw in all of 2025.

The emergency response in Al Bayda has highlighted the scale of the crisis across Yemen and may reflect conditions in areas where MSF is not present. In light of this, health authorities have renewed their call for MSF to expand and intervene in other regions to help address the growing needs.

MSF cannot fill the gaps alone

MSF continues to provide treatment for malnutrition and other medical complications, but emergency medical organisations cannot replace a broader health and nutrition system.

Our teams are treating children today, but we are only seeing the tip of the iceberg, Yemen’s malnutrition crisis requires sustained funding, flexible donor support, and stronger partnerships to meet the scale of the need.
Ainur Absemetova, MSF Head of Mission in Yemen

For thousands of families across Yemen, that hope increasingly depends on whether care remains available when and where their children need it.

Without adequate community and primary health care services, more families may be forced to undertake long journeys for care, and more children may reach hospitals only after their condition has become severe.

Doctors Without Borders/Médecins Sans Frontières (MSF) provides and supports care for children suffering from acute malnutrition and associated medical complications in several locations in Yemen, including Abs General Hospital in Hajjah Governorate, Al-Salam Hospital in Khamer, Amran Governorate, and MSF-supported facilities in Mocha, Taiz Governorate. MSF activities include inpatient treatment for children with severe acute malnutrition and medical complications, as well as ambulatory therapeutic feeding services in locations where these are available.

The figures cited in this article reflect patients treated or identified at specific MSF-supported facilities and should not be interpreted as representative of the overall prevalence of malnutrition in Yemen.

Facebook
Twitter
LinkedIn
WhatsApp
Print

International Activity Report 2025

Dr Hasna Hena Mou and medical assistant Rajib Mazumdar treat a young patient in the emergency room of MSF's Kutupalong hospital.

Médecins Sans Frontières

International Activity Report 2025

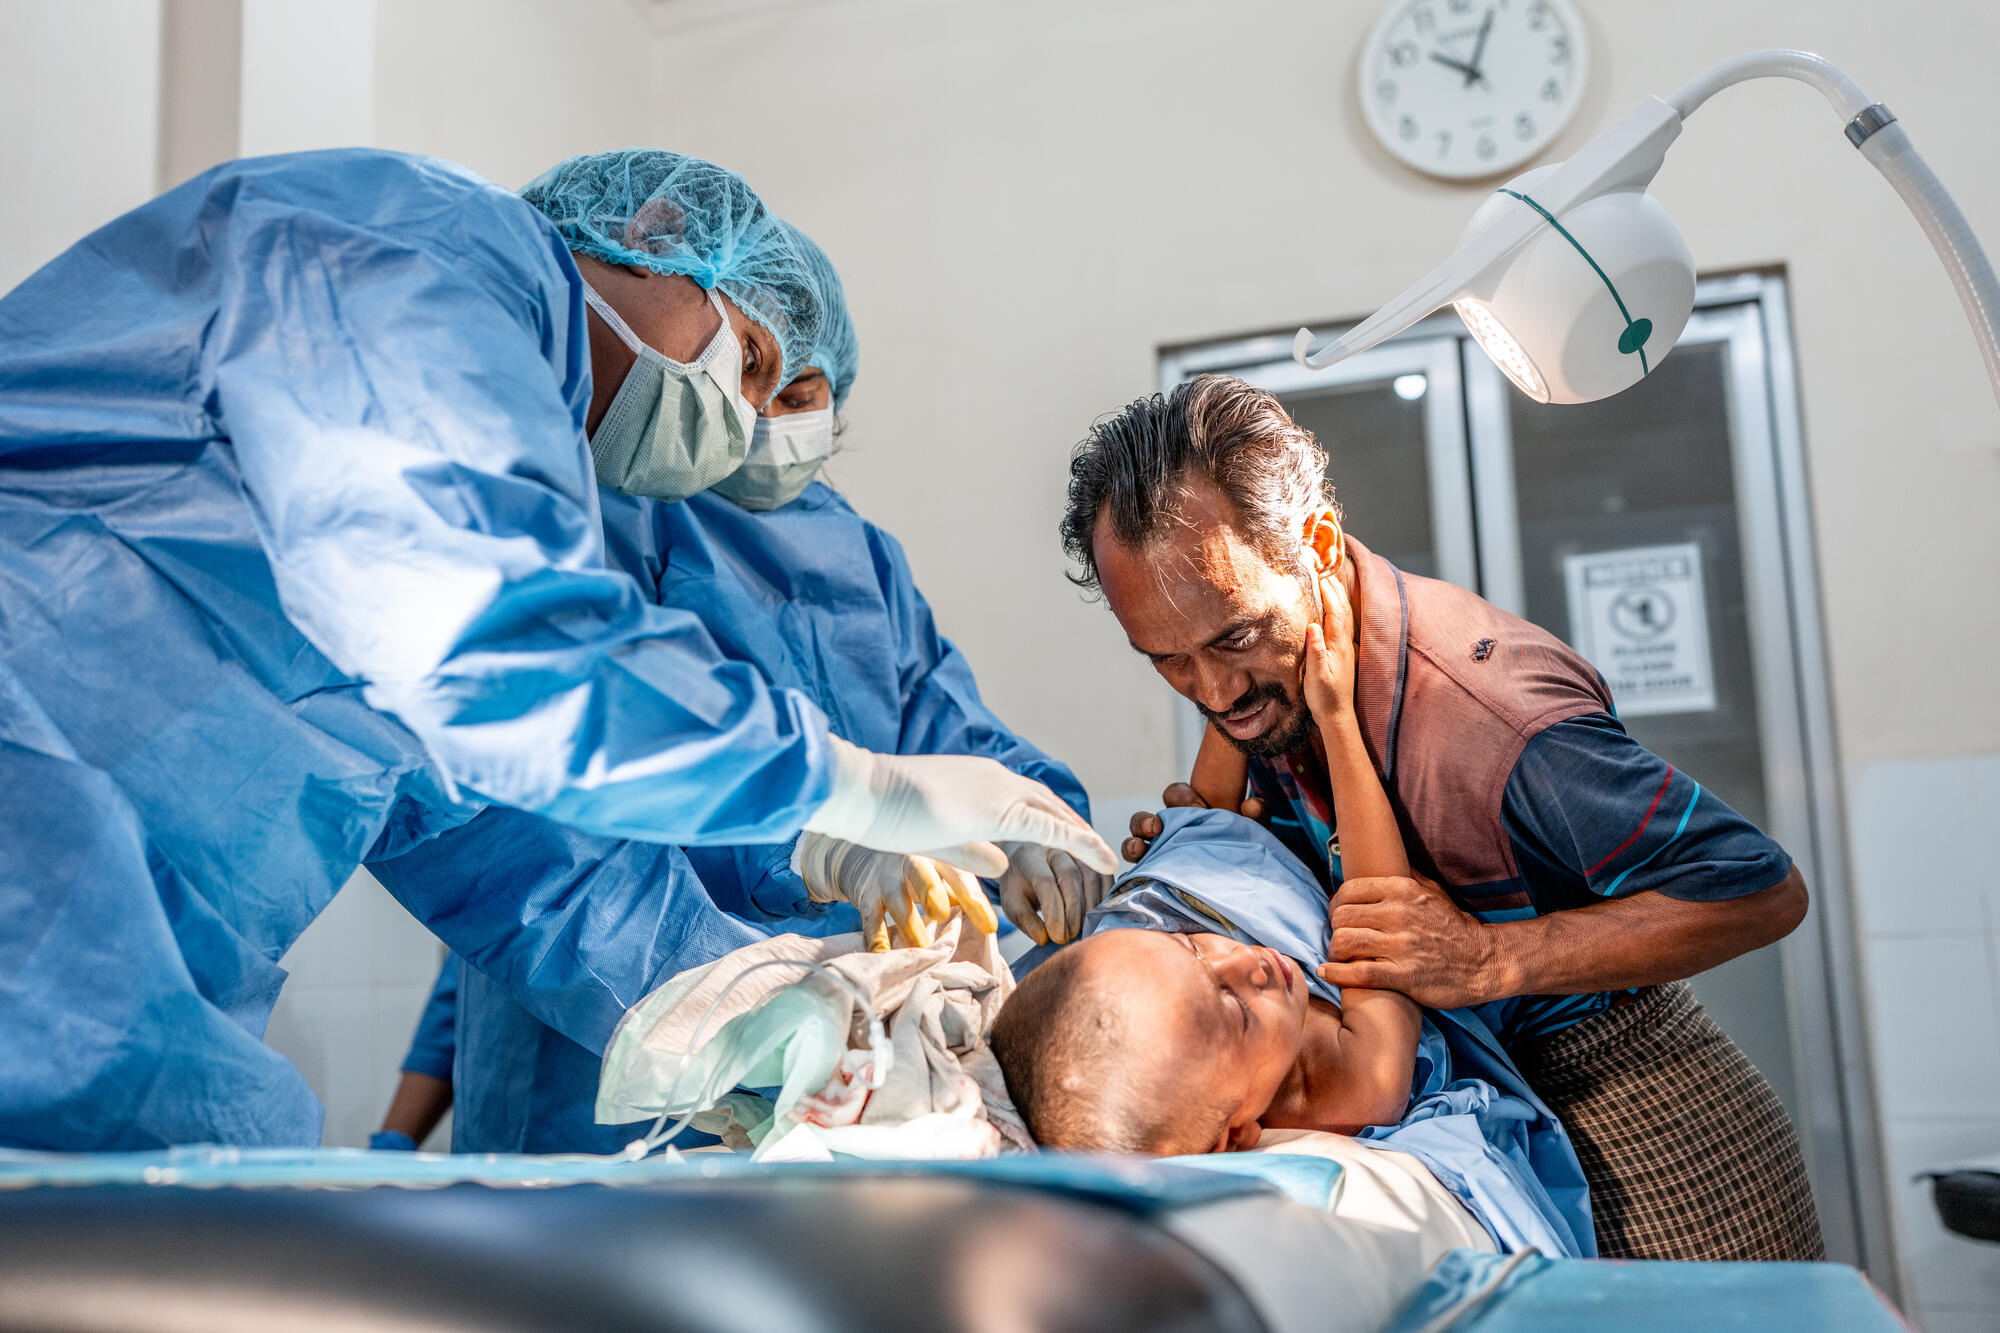
Dr Hasna Hena Mou and medical assistant Rajib Mazumdar treat Shofi Mohammad for abscesses in the emergency room of MSF’s Kutupalong hospital, as Shofi’s father, Anas Mohammad, comforts him. Cox’s Bazar, Bangladesh, May 2025.

© Ante Bussmann/MSF

Share

Foreword

In moments of crisis and exclusion, Médecins Sans Frontières (MSF) teams strive to save lives and alleviate people’s suffering. We provide the care that we can with our colleagues, collaborators, and supporters, but in 2025 we saw growing gaps that are not ours to fill.

When people with power renege on their responsibilities and shared humanity, the communities we serve pay a high price.

In many of the places where we worked, we saw a deficit of accountability that ranged from negligence to flagrant violations of international humanitarian law.

An MSF medical team treats a child in the emergency room of the Kutupalong hospital, Bangladesh.

About MSF

International Activity Report 2025

msf.org17 Jul 2026

2025 in review

The scale of people’s needs – whether due to war, internal instability, disease outbreaks, or the difficulty in accessing medical care – became further highlighted in 2025 amid a climate of aid cuts and anti-humanitarian rhetoric. MSF teams around the world worked to assist people in 72 countries, in an ongoing act of solidarity.

Read more about our activities around the world in 2025

Palestinians gather at a food distribution site in Netzarim, Gaza.

Photo story

A Year in Pictures 2025

msf.org5 Dec 2025

Feature articles

01 / 03

10 Years of UN Resolution 2286: Protect Healthcare

Israeli strike on Nasser hospital in Gaza. © MSF

10 Years of UN Resolution 2286: Protect Healthcare

Ten years after the adoption of UN Security Council Resolution 2286, MSF calls on states to respect their commitment to protect medical care, healthcare workers and humanitarian missions in conflict zones.

Read More
Four Years of Full-Scale War in Ukraine

Damir next to his sister Sasha in Ukraine. © MSF

Four Years of Full-Scale War in Ukraine

Four years of war have deeply affected communities across Ukraine. MSF continues supporting people impacted by violence, displacement and disrupted healthcare services.

Read More

Ebola and DRC: MSF Responds to Ituri Outbreak

MSF teams are responding to the Ebola outbreak in Ituri, supporting patients, infection prevention measures and community health activities.

Read More

Our activities around the world in 2025

Our teams provided medical care in over 70 countries in 2025. Click on the map to find out more.

Loading the map…

    The place names and boundaries used in this report do not reflect any position by MSF on their legal status.

    Facts and figures

    Our activities in figures
    An MSF mobile clinic team examines patients at a transit centre for displaced people in Ukraine.

    17,071,300

    outpatient consultations

    A neonatal nurse checks the vital signs of a newborn baby at the MSF maternity hospital in Khost, Afghanistan.

    405,000

    births assisted, including caesarean sections

    Two MSF doctors review a patient report in the paediatric intensive care unit in Mazar-i-Sharif, Afghanistan.

    2,941,600

    emergency room admissions

    International Financial Report 2025

    Every year we publish our audited combined financial statements. These combined accounts are a means of transparency and accountability, providing a global overview of MSF’s work.

    The International Financial Report represents an aggregation of the financial statements of the 24 sections, 18 branch offices, numerous satellite organisations, and MSF International.

    A woman accompanies her mother to an MSF mobile clinic for people displaced from Sudan in Renk County, South Sudan.

    Annual report

    International Financial Report 2025

    msf.org29 May 2026

    How your donations are used

    Your donations pay for millions of consultations, surgeries, treatments and vaccinations every year.

    Find out more

    • 79%

      Social mission

    • 16%

      Fundraising

    • 5%

      Management & general admin

    Link copied