How Lebanon’s financial troubles have delivered a surge in demand for midwives

How Lebanon’s financial troubles have delivered a surge in demand for midwives

Eva Mousa had always planned to give birth in hospital.

But after the 19-year-old housewife’s husband Mohammad ended up being admitted himself following a motorbike accident, the pair were left financially depleted and indebted. The young, previously middle-class family — newly impoverished, like many in the financially struggling country of Lebanon — have been forced to think of alternative options for childbirth.

With only five months to go until the arrival of their daughter, the young mother said the prospect of incurring further debt influenced their decision to have the pregnancy attended to by a midwife rather than an obstetrician.

They had borrowed from friends and family to afford the cost of Mohammad’s week-long hospital stay and an operation on his leg. It broke them so much financially that Mrs Mousa was left wondering “how on earth could we afford to have a family?”

Following the advice of a cousin who had recently given birth at a midwife-operated clinic in the mountain town of Aley, Mrs Mousa decided to carry her pregnancy to term under the watch of the same midwife.

Her anxiety over deviating from the norm of giving birth in hospital vanished after her first check-up.

“Immediately I was more comfortable than if I had gone to the hospital,” Mrs Mousa said of the quality of care she received. Her daughter Mariam is now a healthy six months old, cooing and smiling under a bundle of blankets.

“I felt like the qabila” — the Arabic term for midwife — “knew exactly what to say and how to act and she was more personable than a doctor.”

The delivery procedure cost the family about 2 million Lebanese pounds or the equivalent of $45 on today’s market rate. By comparison, the average cost of childbirth in a Lebanese hospital is $350 to $500, although some private hospitals charge thousands of dollars.

The cost of childbirth — not to mention pre and postnatal care — has become almost insurmountable in Lebanon’s crumbling economy. Now in its fourth year, Lebanon’s financial meltdown has pushed two thirds of its population into poverty. Inflation is at an all-time high, and the local currency is worth a mere fraction of what it once was. The average public sector employee makes less than $50 a month.

A rise in demand for midwives

A midwife is a qualified and accredited clinical professional who provides specialist care to mothers and newborns. They work with women in labour to enable childbirth, in addition to working with mothers in the prenatal and postpartum stages.

Medical studies on midwifery-led models say the benefits include lowered rates of unnecessary and potentially harmful medical procedures such as Caesarean and labour inductions, higher rates of breastfeeding and significantly increased rates of satisfaction in women when it came to quality of care before, during and after birth.

Most patients cite financial reasons as a major reason for their decision to give birth accompanied by a midwife, Dr Rima Cheaito, head of the Order of Midwives in Lebanon told The National.

The order recorded a “definite increase” in midwife-enabled births following Lebanon’s economic severe downturn, Dr Cheaito said.

Births delivered through midwives in private clinics more than doubled in the first three years of the economic crisis: from 2,095 in 2019 deliveries to 4,800 last year.

It’s a comprehensive service free of charge and open to whoever wants to give birth in the area so long as they fit the criteria
Charlotte Massardier, MSF's advocacy manager

Marginalised and limited despite surging popularity

In Beirut’s Rafic Hariri University Hospital, Lebanon’s largest government hospital, Batoul Al Hamad cradles two day old Yousef. He is her second child to be born with the aid of a midwife.

“Women I knew, neighbours and friends, had told me about their experiences and advised me. But I still had reservations because it’s a different way of giving birth than we’re accustomed to,” the 27-year-old Syrian mother told The National.

“Back then I took their advice and tried it. And here I am again for Yousef, because I’m comfortable here.”

The midwife birthing centre in Rafic Hariri hospital — run by medical NGO Medecins Sans Frontieres (MSF) — became the only hospital-based, midwife-led birthing unit in the nation when it relocated from the Shatila camp for Palestinian refugees in 2018.

According to Public Health Minister and previous director of RHUH, Firas Al Abiad, hosting the unit in a government hospital was partly an initiative to empower the midwife-led model in Lebanon and answer its detractors.

The majority of patients at the birthing centre are Syrian and Palestinian refugees, and domestic migrant workers.

“It’s a comprehensive service free of charge and open to whoever wants to give birth in the area so long as they fit the criteria,” said Charlotte Massardier, MSF’s advocacy manager.

She said MSF staff had witnessed an increase in the number of economically vulnerable Lebanese patients coming to the centre since the start of crisis in 2019.

But with the resources of the Health Ministry and various international aid organisations stretched thin, Dr Al Abiad said there was no capacity to expand the midwife-led model to other hospitals.

“We are looking at how we can even preserve the current model, never-mind expand it, because we’re not sure for how long MSF can maintain it,” he said. The Health ministry was studying ways to independently support the birthing centre, he added.

Aside from the MSF unit, women who desire the care of a midwife must make appointments in private clinics — a significant point of contention for advocates of the practice who say midwives are marginalised in Lebanon’s healthcare system.

Midwives v the system

“As a woman in Lebanon you don’t have many options,” said Dr Tamar Kabakian, a reproductive rights expert and associate professor at the Department of Health Promotion and Community Health at the American University of Beirut. “You have a choice between a midwife clinic and a hospital with an obstetrician.”

Technically and according to Lebanese law, midwives are permitted to be the primary birth attendant in charge of delivering a baby.

But in practice — in part due to Lebanon’s highly decentralised and mostly privatised health sector — critics say midwives have been sidelined, with hospitals regarding them as little more than obstetric assistants.

“The midwife is only permitted to see the mother before and after the birth,” said Dr Cheaito. “And not during deliveries. They’re limiting our role.”

Dr Al Abiad echoed her concern that midwives in Lebanon had “taken a backseat” to physicians, citing numerous studies that found women perceived midwife-led deliveries to be higher quality.

Health experts and advocates of the midwife-led model argue that its numerous economic and health benefits outweigh those of the dominant obstetric model.

In Dr Cheaito’s view, obstetricians and midwives should be working in tandem, with midwives delivering low-risk pregnancies and obstetricians the high-risk.

“If it’s a normal pregnancy and we have highly qualified professionals who can conduct deliveries for a lower cost, why not allow them to work?” she asked.

Midwifery v obstetrics

The obstetric model remains dominant in Lebanon’s vastly privatised healthcare sector.

Dr Kabakian explained that the marginalisation of midwives in Lebanon’s health sector was a “systemic issue” that stems from the struggling Health Ministry’s inability to impose national guidelines and standards of care on the mostly decentralised — not to mention deteriorating — health sector.

As a result, “hospitals have their own standards and practices. It’s different according to each provider and physician,” Dr Kabakian said.

Compounded by Lebanon’s worsening economic crisis, the large gaps and lack of regulation in the healthcare system have conjoined to create an environment where obstetric violence — the mistreatment and abuse of women during childbirth by their care providers — has become a matter of routine.

This includes “interventions that are not medically necessarily and may even be harmful to the mother and child, but are done almost routinely to women in Lebanon,” said Dr Kabakian, “such as episiotomies” — the process of cutting the perineum during childbirth to move the foetus through the vaginal opening more easily — “and caesarean sections. Women don’t know when they don’t need C-sections and care providers do it because it’s faster.”

Lebanon has one of the highest rates of caesarean sections in the world, hovering at about 50 per cent according to the World Health Organisation. They are not needed nearly as often as they are prescribed but are faster than normal deliveries and therefore more convenient for obstetricians. The procedure also incurs additional fees, which means more revenue for the hospital or doctor.

Overwhelmed physicians who are paid per-service and cash-strapped hospitals have little incentive to advance the midwife-led model, instead maintaining an obstetric model that priorities the needs of the doctor over the patient.

“This is a private, fee-for-service healthcare system,” said Dr Al Abiad of the challenges of bringing midwifery to the foreground in hospital settings. “Physicians are obviously not very happy to give up that route. At the end of the day, this is a source of income for them.”

By contrast, midwives attend to and prioritise the woman’s needs, “leading to an improved quality of care,” said Dr Kabakian. “It’s the healthier option, scientifically-speaking.”

Health advocates argue that a strong midwifery-led model might be able to reduce the impact of the economic crisis on patients.

“We could have higher value deliveries at lower cost to the patient,” said Dr Abiad. “This economic crisis is an opportunity for us to rethink our care delivery.” He added that he was eager to dispel perceptions that “midwife-led delivery is lower quality because it’s more affordable. That is not the case.”

But for mothers such as Mrs Moussa and Mrs Al Hamad who were driven to using midwives for financial reasons, it is also the comfort and quality of care which will keep them loyal to midwives.

“She was with me before and after I had Mariam,” Mrs Mousa told The National. “She told me how to care for her in the first few weeks. That I should stay warm and drink natural juice to maintain my body’s nutrients while breastfeeding.”

“I’ll definitely go to her if I get pregnant again.”

*First published in The National News

MSF supports Haitian health authorities in cholera vaccination

MSF supports Haitian health authorities in cholera vaccination

Port-au-Prince, 20 December 2022 – Médecins Sans Frontières (MSF) teams in Haiti are supporting the cholera vaccination campaign launched by the national health authorities. This campaign is the latest effort in response to the resurgence of the disease, which has affected more than 15,000 people and caused more than 300 deaths in the country since the end of September. On 12 December, the Ministry of Public Health and Population (MSPP) received 1.17 million doses of cholera vaccine from the International Coordinating Group, a mechanism to manage and coordinate the provision of emergency vaccine supplies to countries during outbreaks.

“We support the vaccination campaign in Cité Soleil, one of the most cholera-affected areas of Port-au-Prince”, says William Etienne, MSF emergency coordinator. “Our teams are helping with the transportation of the vaccine doses and other items, facilitating the movement of the MSPP vaccination teams, distributing soap and other hygiene items, and taking care of waste management.”

The ongoing cholera resurgence comes at a time when the population is already facing enormous difficulties in accessing health care. Fuel is becoming progressive available after weeks of extreme scarcity due to the blockage of the main oil terminal, but insecurity and violence combine with an unprecedented economic and social crisis to make access to basic services extremely complicated.

“Though the pace of contamination has apparently slowed down recently, vaccination remains a very useful tool in a fragile health context such as this” says William Etienne. “Haiti has been hit by a major cholera epidemic in recent past”. MSF teams have been part of the cholera emergency response since the first few patients were identified. We quickly opened several cholera treatment centres in Port-au-Prince and in the Artibonite province, work to provide access to clean water and run health promotion activities.

Lebanon’s ailing health system grapples with cholera outbreak near Syrian border

Lebanon’s ailing health system grapples with cholera outbreak near Syrian border

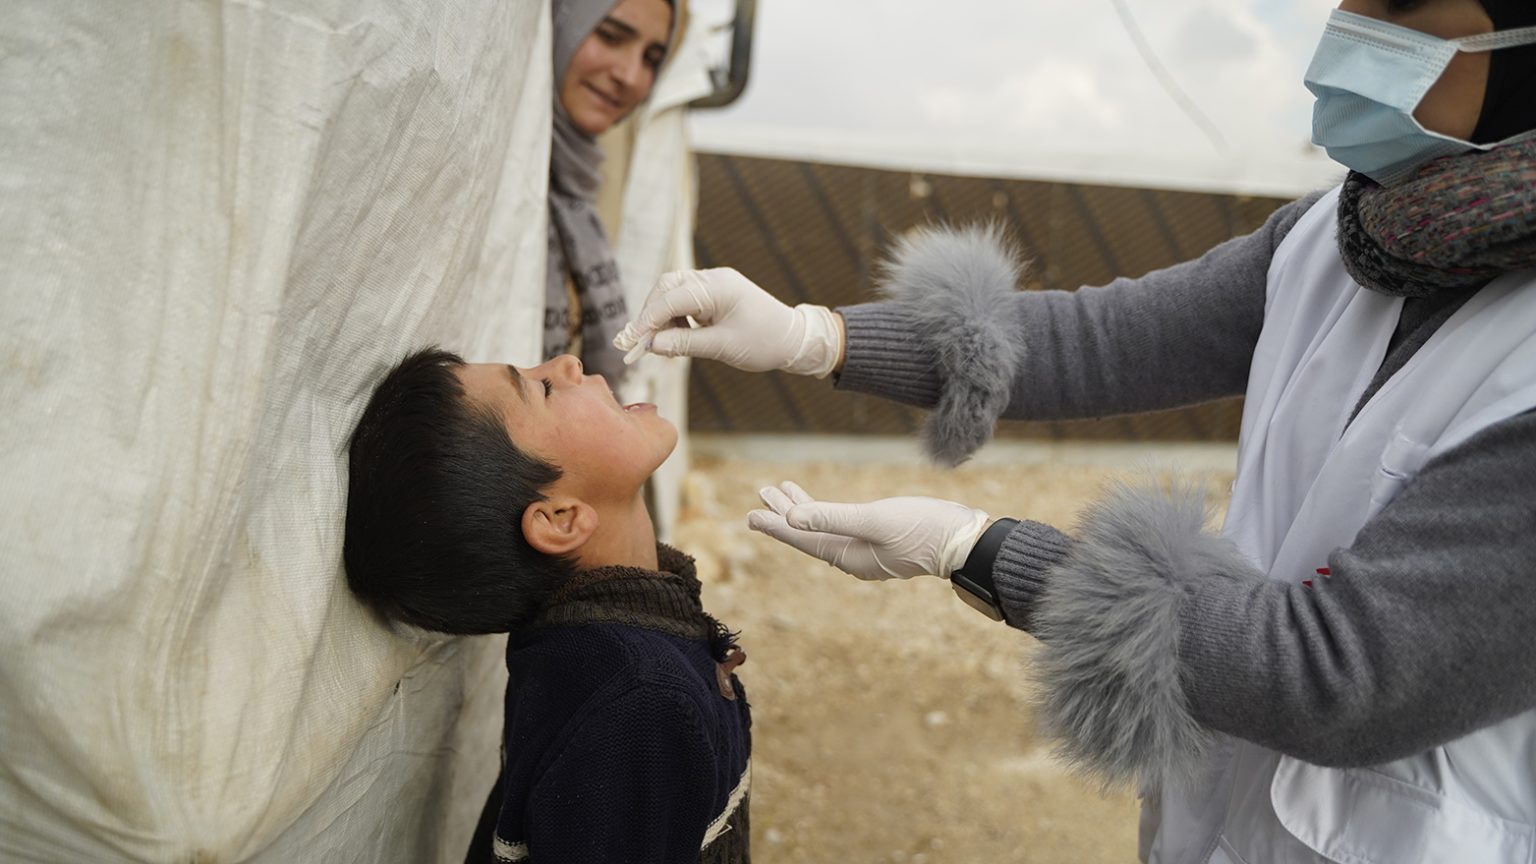
In a freezing classroom in Arsal, an isolated Lebanese town perched 1,500 metres above sea level near the Syrian border, one by one children line up for their cholera vaccine — taken orally, a quick gulp down the throat.

The teacher marks their hands with a pen, and now the jacket-clad children have an extra layer of protection against Lebanon’s first cholera outbreak in three decades.

Arsal, a largely Sunni Muslim town in the north-eastern reaches of the Baalbek-Hermel governorate, is one area of Lebanon that has been a focal point of the cholera spread — and efforts to fight the disease.

A poor, overcrowded town where informal settlements sit alongside houses, it’s the perfect place for the disease to take hold.

And while Lebanon is — at the moment largely successfully — countering cholera, there are fears that the looming winter could isolate Arsal, where the proportion of Syrian refugees is double that of the Lebanese population.

By the end of November nearly 450,000 vaccines had been administered. Since the outbreak in early October, there have been about 4,600 suspected or confirmed cases and 20 deaths.

The cholera strain found in Lebanon is similar to the one in neighbouring Syria, itself struggling with a much larger outbreak.

The World Health Organisation describes cholera as “an acute diarrheal disease that can kill within hours if left untreated”.

It can be easily treated with oral rehydration salts but in severe cases immediate medical attention is needed.

Lebanon’s economic crisis means the country lacks a sufficient supply of medicine, clean water and electricity.

Organisations such as Medicines Sans Frontiers, which recently opened a cholera treatment unit in Arsal, are going door-to-door in a bid to get people vaccinated.

One of those to take the vaccine was the family of Salah, a middle-aged Lebanese man from Arsal who lives near one of the small refugee camps that merge with the older homes.

Normally the family gets their water from lorries and a nearby well.

“You never know. Waste management is not properly functioning, so you never know if this water is clean or if the water in the well is clean,” he said.

Salah said waste management and infrastructure were already in a bad state before a series of crises hit Lebanon, including a devastating economic crisis that first became apparent in 2019 and an influx of refugees fleeing the war in nearby Syria that began more than a decade ago.

“It became worse with overcrowding but it was already bad,” he added.

For now, suspected and confirmed cholera cases are somewhat stable — and are even potentially going down slightly, according to government statistics.

The focus has been on prevention — whether through awareness or efforts to ensure that the water is safe — and on treating those who fall sick.

While cases have largely not been as severe as initially predicted, fears remain that cholera could be around in Lebanon for longer. It is also believed that Lebanon’s health system would struggle to tackle a larger or more serious outbreak. So, the focus is on ensuring that it does not become an epidemic, said Farah Nasser, medical co-ordinator for MSF Lebanon.

“If we want to describe [the situation] it would be we are still in control, as the cases are still mild to moderate. The phase we are in now, we still have the hospitals prepared, there are still places in the hospitals. So it is still under control,” she said, contrasting the current situation to that when cholera first broke out in Lebanon when authorities and humanitarian organisations had to rapidly mobilise.

“But now it is controllable and we are having the time to really work on the prevention arm of the outbreak. The idea is we should focus really on prevention. If we really worked on prevention, then we will be in a good place.”

Lebanon’s economic capitulation has been described as one of the worst in modern history by the World Bank, with much of the population plunged into poverty. It has led to shortages of vital medicine, a lack of clean water and hospitals impaired by power cuts.

“The health system is under the burden of all the crises,” said Ms Nasser. “We had a good health system, which was mostly private plus what the Ministry of Public Health was working on as primary healthcare centres.

“And then with the economic crisis, it put a huge burden on that system, which is near collapse. They are not getting what they need [financially] and it’s a huge burden on the patients themselves.”

All of Lebanon’s eight governorates have detected cholera, but it is most prominent in the areas neighbouring Syria, where the border between the two countries is porous. While Akkar to the north-west of Arsal has recorded more cases, the latter is bereft of a public hospital — although MSF does operate a clinic — and relatively isolated.

Akkar and Arsal, which briefly came under the control of ISIS in 2014, have particularly weak infrastructure and their residents have particularly poor access to clean water.

Winter is expected to be grim in impoverished Arsal — previous years have seen refugee camps covered in blankets of snow amid below freezing temperatures.

One family The National spoke to said they were forced to burn plastic to fuel their heater, despite the fact that it would likely worsen a heart condition of one of their young children.

Recent flooding, blamed on blocked pipes, was yet another issue to hit the area.

One of those affected was Raida, a mother of five who lives in a Syrian refugee camp in Arsal that was flooded. She was in an isolation unit and had taken her youngest — only three months old — to the MSF clinic when she had diarrhoea, a classic symptom of cholera.


“Two days ago I realised I was changing her diapers more than usual,” Raida said.

For now, Lebanon’s embattled health system is responding — but a wider, more serious outbreak could prove too much.

“With a bigger outbreak, I think we would be not in a good place,” said Ms Nasser. “The efforts since day one to prepare government hospitals to accept patients … most of the hospitals were prepared within the first two weeks of the outbreak.

“But if we had a really large outbreak, as we’ve seen in other countries, that would be a super-big burden on our health system.”

* First published in The National News

Iraq: Bridging the gaps to curb the spread of Crimean-Congo Hemorrhagic fever

Iraq: Bridging the gaps to curb the spread of Crimean-Congo Hemorrhagic fever

CCHF is a viral disease that causes severe haemorrhagic fever, with a 10 to 40 per cent case fatality rate. The hosts of the virus usually include a wide range of animals, such as cattle, sheep and goats. The transmission from animals to humans happens through tick bites or close contact with the body fluids of infected individuals or animals.

2021 saw a significant increase in CCHF in Iraq compared to previous years, with 33 cases reported and 13 deaths as a result. Within the first five months of 2022, the Iraqi Ministry of Health reported 212 suspected and confirmed cases. Of these, 27 people died. By mid-August, an additional 87 patients and 28 deaths were reported. “We immediately offered our help to the health authorities and identified key areas where we could offer MSF’s valuable experience in responding to outbreaks of haemorrhagic fever worldwide,” says Dr Chen.

Although the current CCHF trend shows a significant drop in the number of cases compared to the first half of 2022, MSF is still in contact with Iraqi health authorities and is closely monitoring the situation. “We are still on high levels of preparedness in case the numbers start rising again,” adds Dr Chen. “New batches of medications are already on the way to be donated to the Ministry of Health.”

“We knew Crimean-Congo haemorrhagic fever (CCHF) was present in Iraq decades ago. But comparing the current and historical epidemiological data, we saw that the spread of CCHF was happening faster than usual this time,” says Dr Chen Lim, MSF’s medical coordinator in Iraq.

Timely response and effective collaboration

As an emergency medical humanitarian organisation, our teams are ready for rapid responses to health and humanitarian crises. With the CCHF outbreak, our team in Iraq worked closely with the health authorities in the capital and the local health authorities in the Dhi Qar governorate, the outbreak’s epicentre. Our aim was to control the spread of the disease and treat those affected by it while ensuring that healthcare providers were well protected. Three essential pillars of intervention were needed at that stage: prevention, awareness and medical supply.

Technical capacity building of healthcare providers

“The key area of our intervention focused on training healthcare providers and their supporting staff on ensuring proper infection prevention and control (IPC) while engaging with patients suffering from CCHF. This is an essential element for frontline workers,” explains Dr Chen.

In parallel to IPC, MSF teams also worked on increasing healthcare providers’ capacity in clinical case management by conducting training sessions on diagnosing patients and providing them with proper treatment and support. This included laboratory testing methods, treatment options, techniques and approaches.

Rapid supply of essential medications

While the oral form of the drug Ribavirin – the drug of choice to treat CCHF – was already available in Iraq, this was not suitable for all patients. In severe cases, some patients might not be conscious, making it impossible to take the medication orally. On top of that, oral medications require more time until their effect occurs. The injectable form of the drug is therefore more efficient and lifesaving to many patients but was not available in Iraq at the time. After our recommendation to procure the drug, Iraqi authorities acted swiftly. “We were delighted to see the rapid response when we offered to import the medications from our existing international stock,” says Dr Chen.

Within a relatively short time, MSF imported 10,000 vials of Ribavirin and provided the technical support to healthcare providers to ensure the effective administration of the medication to patients.

Community awareness and health education

To limit the spread of the disease at the source, community awareness and health education are essential. For the community in Dhi Qar, MSF used social media to raise awareness about CCHF. “We know that people in Iraq rely heavily on social media platforms as a source of information,” says Dr Chen. “We worked on identifying information gaps within the community to develop engaging campaigns and disseminate key self-protection messages to the people living in Dhi Qar. Our social media campaign was two-way, meaning that people had the opportunity to ask us questions, and we responded to them.” Through these campaigns, MSF reached more than 1,1 million people in Dhi Qar within three weeks, which proved to be a remarkably efficient way of disseminating multiple health awareness messages in a short time.


According to data from the World Health Organisation[1] (WHO), the first cases of Crimean-Congo haemorrhagic fever (CCHF) in Iraq date back to 1979, when 10 patients were diagnosed with the disease. Since then, the number of detected cases has been low and infrequent. Between 1989 and 2009, only six patients were reported. In 2010, 11 cases were detected, followed by three deaths in 2018.

[1] World Health Organization (1 June 2022). Disease Outbreak News; Crimean-Congo Haemorrhagic Fever in Iraq. Available at: https://www.who.int/emergencies/disease-outbreak-news/item/2022-DON386

COP27: Joint Statement with ICRC

COP27: Joint Statement with ICRC

The triple threat of climate change, conflict, and health emergencies: A deadly mix for the most vulnerable in fragile settings.

Geneva (MSF/ICRC) – Climate change is not a distant threat. It is already dramatically affecting vulnerable people across the globe. In particular, the changing climate is having devastating consequences for people living in conflict situations and those who don’t have access to basic health care.

Médecins Sans Frontières/Doctors Without Borders (MSF), the International Committee of the Red Cross (ICRC), and the Red Cross and Red Crescent Movement are working closely with communities in countries where the convergence of climate change, armed conflict and health emergencies is a grim reality. Of the 25 countries most vulnerable to climate change and least ready to adapt, the majority are also experiencing armed conflict. In many of these locations, people lack access to basic healthcare. When climate shocks occur in countries with limited food, water and economic resources, people’s lives, health, and livelihoods are threatened.

Somalia has suffered through an erratic cycle of droughts and floods in recent years, exacerbating an already dire humanitarian situation further complicated by three decades of armed conflict. People have limited time to adapt because the shocks are so frequent and severe.
Humanitarian organisations have also been responding to flooding in South Sudan and across the Sahel; devastating cyclones in Madagascar and Mozambique; and severe drought in the Horn of Africa. The climate crisis worsens health and humanitarian crises.

As humanitarians, we are alarmed by the current reality and projections for the future. We see droughts, floods, insect plagues and changing rainfall patterns which can all jeopardise food production and people’s means of survival. We see more extreme and more powerful weather events such as cyclones which destroy essential health infrastructure. We see changing patterns of deadly diseases such as malaria, dengue and cholera. Conflict and violence increase the need for emergency health assistance while also limiting the capacity of health facilities.

All these situations are occurring in a world that has warmed 1.2 degrees above pre-industrial levels, as we witness how the world’s most vulnerable pay the deadly price of a problem overwhelmingly caused by the world’s richest nations. Additional warming will lead to disastrous consequences unless urgent and ambitious mitigation measures are taken and adequate support is mobilised for the most affected people and countries so they can adapt to growing climate risks.

“Today, needs are already outstripping the response. This is a crisis of solidarity and it is now giving way to a crisis of morality. The world cannot leave those suffering the most tragic consequences without support,” said Stephen Cornish, Director General of MSF Switzerland.

Financial and technical support must reach people who need it the most which are not happening at the scale it should. The Paris Agreement’s commitment to increase support for the least developed countries fails to acknowledge that a significant number of them are also affected by conflict and should be prioritized. To date, promises have not been met to reduce carbon emissions and support countries experiencing the biggest impacts.

“We’re seeing the severe compounding effects of growing climate risks and armed conflict from Afghanistan to Somalia, Mali to Yemen. Our work in these places helps people cope with the climate crisis. But humanitarian actors cannot respond alone to the multitude of challenges. Without decisive financial and political support to the most fragile countries, the suffering will only worsen,” said Robert Mardini, the ICRC’s director-general.

We are calling on world leaders to live up to their commitments under the Paris Agreement and Agenda 2030 and ensure that vulnerable and conflict-affected people are adequately supported to adapt to a changing climate. We must collectively find solutions and ensure access to adequate climate finance in challenging environments. Leaving people behind is not an option.

Infection Prevention and Control procedures in low-resource contexts

Infection Prevention and Control procedures in low-resource contexts

Infection prevention and Control (IPC) is directly linked with patient safety and high-quality healthcare, but in low-resource or conflict-affected settings there are difficulties and barriers that prevent establishing effective IPC measures. Efficient infection prevention and control (IPC) is crucial for stopping the spread of preventable healthcare-associated infections as well. Effective IPC programmes, according to the World Health Organization (WHO), can lower HAI rates by 30%. For the IPC week that takes place from October 16th till the 24th, Dea Abi-Hanna, IPC Mobile Implementation Officer, explains to us more about IPC and what limits low-resource countries from implementing effective IPC programmes.

  • What is the main role of an IPC specialist?

Infection prevention and control (IPC) focal points or specialists are trained professionals from diverse backgrounds, including nursing, midwifery, medicine, public health, pharmacy and allied health fields. IPCs work on the frontlines to prevent and manage infections in healthcare facilities and support community-based interventions, by promoting a culture of safety and impact the health of patients, staff and families.

  • What are some of the most important things you do to maintain a safe environment for patients and yourself?

Patient safety, which is the cornerstone of quality patient care, includes preventing errors and the harm they bring to patients. Providing safe patient care is a necessary component of providing high-quality healthcare. To protect both patients and medical staff, it is crucial to prevent infection and cross-infection. Infection-causing organisms, such as viruses and bacteria, are relatively simple to spread from one site to another and, eventually, from one person to another. It is crucial in daily life, but it is much more crucial in the healthcare setting where patients can have compromised immune systems or open wounds that leave them exposed to infection.

In our daily life, each individual can definitely avoid spreading and contracting diseases by taking precautions and by acting responsibly; such as maintaining good hand hygiene, following good food hygiene practices, getting vaccinated when required, only using antibiotics if your doctor decides that you need them, and by keeping an eye out for infections and their side effects.

  • What did we learn after the Covid-19 pandemic regarding IPC? And are those lessons carried out nowadays?

The world has changed significantly since 2020, and we have discovered considerable infection prevention and control (IPC) gaps, particularly among health care professionals who are more at risk and require more protection and training. Additionally, this pandemic demonstrated to us that individuals have short memories and that things that are not always around fade quickly. Therefore, I would say that we need to keep the Covid-19 pandemic experience in our minds and invest in infection prevention at the community level and in healthcare settings; Individuals should maintain a responsible behaviour and attitude to prepare for any possible risks by adhering to appropriate and credentialed recommendations to prevent infections and diseases.

  • Do you see a need for IPC awareness in the middle east? Among patients or healthcare workers?

The need for more education and awareness among patients, their families and healthcare workers should always be initiated regardless of the type of healthcare facility—a hospital or a clinic. Unfortunately, noncompliance with IPC procedures has a considerable negative impact on the environment of care, patient protection, and healthcare worker safety; and continuous efforts are being made to overcome this barrier both in the Middle East and across the world.

  • Where do you see the main problem in achieving full awareness? And how it can be achieved?

Any healthcare facility in the world can access guidance documents and recommendations, but the implementation will vary widely depending on the context. For instance, there are clearly difficulties in the development of successful IPC programmes in low-resource settings – healthcare facilities are frequently affected by poor IPC leadership, including inadequate financing for IPC activities and specialized, dedicated workers, a lack of IPC policies and procedures and insufficient resources due to budgetary constraints. Many hospitals still lack basic infrastructure, including measures and treatments for unclean water, sanitation, and hygiene, lack of IPC training for staff, poor compliance to IPC procedures like hand hygiene, environmental cleaning and disinfection, and reprocessing of reusable medical equipment, as well as inadequate infection surveillance systems. All these are critical barriers to effective IPC in low resource settings.

In conflict-affected settings, the access to healthcare, water, and sanitation, as well as the need for emergency surgical and medical care, are all significant local constraints and barriers that prevent effective IPC. These constraints and barriers also have a significant impact on the rise in healthcare-associated infections, particularly surgical site infections and antimicrobial resistance.

A plan, leadership toward one goal—patient and staff safety—as well as administrative commitment are all necessary for the establishment of effective infection prevention and control measures. Minimal resources may be employed to accomplish this. It is as possible to implement appropriate IPC procedures in low-resource contexts as it is in high-resource ones.

Website (2000 × 1333px) (13)

IPC should become a daily common practice not only during this week, together we can all prevent, control infection and save lives.

LEBANON: Lack of safe water and sanitation threatens the ability to contain the spread of cholera

LEBANON: Lack of safe water and sanitation threatens the ability to contain the spread of cholera

The first cholera outbreak in nearly three decades in Lebanon, is unfolding on top of the ongoing economic and fuel crisis that has further exacerbated the already limited access to safe drinking water and proper waste management networks in the country, threatening a full-blown spread of the disease. The already old and weak waste management networks are not regularly maintained and are leaking into the streets and households. Electricity shortages have forced power-dependent water pumps to stop working for an extended period causing water taps in homes to run empty. 

As a result, people are relying on unregulated water trucking to get their water supply. Restricted by the financial crisis, other people, mainly in overcrowded and poor settings who are unable to afford private water supply, are sourcing water from polluted rivers, and ponds to cover their needs. In parallel, shortages of medical supplies and diagnostics are hampering people’s ability to access hospital care

Since the beginning of the outbreak, Médecins Sans Frontières /Doctors Without Borders (MSF) has been increasing its efforts in the country to support in the curb of the outbreak and treating patients.

MSF’s experience working in more than seventy countries facing medical emergency crises, such as cholera, for the past fifty years allows us to act fast and put in place a comprehensive strategy to extend our support to the national health authorities, and people in Lebanon, in their fight against cholera”, says Dr Caline Rehayem, MSF Medical Coordinator in Lebanon. “We know for a fact that cholera isn’t complicated to manage, as long as the right tools are put in place: from prevention, to treatment”, she adds.

Since declaring it an outbreak on October 6, 19 people have died as a result of the disease, with the number of confirmed and suspected rising to 3,671 as of 16th of November 2022.

Responding to the Outbreak: Patient Care & Vaccination

In the Bekaa Valley, MSF adapted a unit in its hospital in Bar Elias to be able to receive and treat cholera patients with a capacity of 20 beds, that can increase as needs arise. Since its opening on 31 October, we have received thirty three patients in our cholera treatment unit. The required adaptions made to the unitensures that the other services in the hospital, mainly for essential surgeries and wound care, can continue to run. MSF is also opening a field hospital with a capacity of twenty beds soon in Arsal, an area in the northern east of Lebanon where the nearest public hospital is at least forty kilometres away.

To limit the spread of the disease, MSF is vaccinating against cholera in Arsal, Tripoli, Akkar, and Baalback- Hermel in the north and north east of Lebanon as part of the three-weeks national vaccination campaign launched by the health authorities in the country. MSF is focusing on these areas that are poor and overcrowded where diseases such as cholera can spread more rapidly, putting people living there at heightened risk. In one week, our teams have managed to vaccinate 14,224 people and are targeting 150,000 people in total.

The vaccination activities are taking place as part of a coordinated effort between the Ministry of Public Health, international and local organizations to administer 600,000 cholera vaccines received by Lebanon, as first phase procurement, to combat the recently declared cholera outbreak in the country.

Spreading awareness in the community & training healthcare workers

Since the last recorded case of cholera in Lebanon was in 1993, raising awareness about how the disease is spread and how to treat it, is a vital step to contain the disease. MSF teams are going from door-to-door in the Bekaa Valley, north, and northeast of the Lebanon walking across neighbourhoods, visiting homes, shops, and camps actively seeking out people to raise awareness on the disease and the prevention measures to be taken.

“We provided training to healthcare workers and community health workers among various actors in an effort to support the healthcare system and communities to cope with the outbreak”, says Dr Caline Rehayem.

So far, we provided more than 17 trainings to a combination of 148 medical and paramedical personnel.

Prevention Measures, and Patient Care are essential, however not enough

Enhancing cholera prevention measures, cholera vaccination and patient care are all critical elements when responding to a cholera outbreak. However, cases of cholera and other waterborne infectious diseases are expected to regularly resurface and spread further if no meaningful actions are taken to ensure people’s access to safe drinking water and sanitation services in the country.

It is a scientific fact. Cholera is caused by ingesting bacteria of faecal origin – Vibrio cholerae – found in dirty or stagnant water, and for it to be properly contained, the root of the problem must be solved” underlines Marcelo Fernandez, MSF Head of Mission in Lebanon. “Otherwise, the current dire water infrastructure in Lebanon will continue to expose the population to highly contaminating diseases such as cholera.

LEBANON: MSF Starts Cholera Vaccination amid Threat of a Full-blown Spread of the Disease

LEBANON: MSF Starts Cholera Vaccination amid Threat of a Full-blown Spread of the Disease

Beirut, 15th of November 2022 – Médecins Sans Frontières /Doctors Without Borders (MSF) is contributing to the national vaccination campaign against cholera launched by the Lebanese Ministry of Public Health’s by vaccinating people in Arsal, Akkar, Tripoli and Baalbak – Hermel in the north and northeast of Lebanon where most cholera cases are registered in the country. 600,000 cholera vaccines received by Lebanon, as first phase procurement, are to be administered in coordination with various international and local actors.

“MSF has started vaccinating since five days and, so far, we have managed to vaccinate 6,677 people”, says Marcelo Fernandez, MSF Head of Mission in Lebanon. “Our teams are going from door to door in all neighbourhoods, visiting homes, shops, and camps actively seeking out people to get vaccinated and to raise awareness on the importance of vaccination of a rapidly spread disease.”

Since Lebanon recorded its first cholera case in almost three decades on October 6th, 18 people have died as a result of the disease, with the number of confirmed and suspected cases rising to 3,395 as of 14 November 2022.

MSF’s vaccination efforts are targeting Lebanese and refugees living in poor and/or overcrowded areas in the country, conditions that put people at heightened risk of contracting infectious diseases.

“To be able to effectively curb the outbreak, it is crucial to enhance cholera prevention measures, of which vaccination is one of the critical elements”, explains Marcelo Fernandez. “However, if no meaningful actions are taken to ensure people have proper access to safe drinking water and sanitation services in the country, we can expect cholera and/or other waterborne infectious diseases to resurface regularly in Lebanon” adds Fernandez.

In addition to administering cholera vaccines, MSF is also providing patient care. In the Bekaa valley (Bar Elias and Arsal) MSF is running two cholera treatment centres with a total capacity of seventy beds. In Tripoli, north of Lebanon, and Arsal, oral rehydration points are being set up for people who do not require hospitalization. Five medical kits were procured by MSF to treat up to 3,125 cholera patients.

MSF is also providing technical training to Lebanese health workers on the treatment of cholera patients, mobilised teams to raise awareness about the disease and distributed hygiene kits to help people maintain essential household and personal hygiene in the Bekaa Valley, north, and northeast of Lebanon (Bar Elias, Akkar, Baalbak-Hermel, and Arsal).

World Diabetes Day 2022: Unlocking (DTx) – The Diabetic Patient Support App

World Diabetes Day 2022: Unlocking (DTx) – The Diabetic Patient Support App

Its very unfortunate that in the 21st century there are still huge gaps in the healthcare systems in low-to-middle income countries. Medical gaps ranging from non-existing healthcare services to low ratio of healthcare workers to population. The Covid-19 pandemic exacerbated those gaps even more.

However, with adapting Digital technology there is a huge potential to improve countries’ responses to infectious-disease threats and to strengthen primary healthcare, such as Diabetic care.

It is currently estimated that 80 per cent of annual mortality related to non-communicable diseases (NCDs) occur in low- and middle-income countries, according to the WHO. The prevalence of diabetes is high across the Middle East and North African (MENA) region, constituting an increasing public health problem. Lebanon is one of the countries in the region that has experienced a sharp rise in the burden of NCDs, including diabetes, over the last decade. In Lebanon, the estimated prevalence of diabetes in 2021 for people aged 20-79 years is 396 per 1000 people, and it is predicted to increase to 469 per 1000 by 2030, according to data from the International Diabetes Federation. 

Due to socio-economic factors and the complex nature of diabetes management adherence to medication among people living with diabetes in low-resource settings is suboptimal. Individuals living with type 1 or type 2 diabetes are also at increased risk for depression, anxiety, and other mental health disorders. These compounding factors lead to poor glycemic control, clinical outcomes, and quality of life. There is a clear demand for improved systems that provide support to patients living with diabetes to increase their ability to confidently self-manage their condition and improve their treatment experience and their physical and mental health and wellbeing.

The Digital Therapeutics (DTx) for Diabetes case, initially launched by the MSF Sweden Innovation Unit (SIU) and the Operational Centre Geneva (OCG) in 2021 in collaboration with NCD clinicians and patients in Greece and Lebanon clinics, aiming to both deliver a patient support intervention and understand  how DTx may supplement current MSF practices. More specifically this project seeks to:

  1. Assess the needs of patients living with Diabetes (Type 1 and Type 2) who are undergoing treatment in MSF clinics in the Bekaa Region, Lebanon.
  2. Co-create a patient support intervention including a DTx and clinician management dashboard alongside patients, their caregivers, and MSF clinical and operational experts.
  3. Implement an intervention which integrates with the MSF Lebanon system to build patient understanding and confidence in self-management practices.
  4. Generate evidence of patient-perceived quality of care (QoC) and patient outcomes.
  5. Establish a replicable pathway for scaling DTx interventions across MSF and beyond in humanitarian and global health contexts.

MSF has an immense opportunity to improve health access and quality of care through patient-centred digital health interventions such as DTx. We believe that evidence-based health solutions can provide a new perspective and lead to big improvements in a healthcare system to provide access to safe, effective and affordable medical services.

MSF Lebanon hospital adapted to care for cholera patients

MSF Lebanon hospital adapted to care for cholera patients

As part of its continuous and ongoing efforts to fight the cholera outbreak in Lebanon, Médecins Sans Frontières (MSF) has adapted its hospital in Bar Elias, in the Bekaa valley, to receive and treat cholera patients with an initial capacity of 10 beds, which can be expanded according to the needs. With the adaptations done, the hospital will continue to function for urgent surgical procedures.

Since the declaration of the outbreak in Lebanon on the 6th of October, MSF has increased its efforts in various regions of the country, including Tripoli, Akkar, Bekaa and Beirut, to support the communities and the Lebanese Ministry of Public Health in the curbing of the cholera spread. 

MSF teams are simultaneously carrying out needs assessment for supporting the setting up of other cholera treatment facilities in the most affected areas. The teams are also sharing their expertise in the management of cholera outbreaks with other local and international actors in the country through trainings and sharing of experiences according to the international protocols. This is due to MSF’s longstanding 50 years of experience in emergency settings throughout the world, and years of experience with cholera prevention and treatment.

This cholera outbreak is happening at a time when Lebanon is faced with an economic crisis with dire consequences on the medical response, the proper maintenance of the waste management and water networks, as well as its impact on people’s access to safe and clean water. “Local and international actors in Lebanon are needed at this time to put forth and prioritize the necessary measures for ensuring safe access to clean drinking water, and safe water and sanitation supplies for everyone”, says Julien Raickman, MSF Head of Mission in Lebanon. 

In addition to the hospitalisation capacities in Bar Elias, other MSF clinics in Akkar, Northern Bekaa, and South Beirut are getting equipped with oral rehydration points, “and we are also supporting designated health care facilities to manage patients seeking medical attention for acute watery diarrhoea.” Adds Reickman.

 It is worth noting that most of the cholera infected patients do not report severe symptoms. However, it remains vital not to delay seeking medical care in case of acute watery diarrhoea as starting rehydration treatment early is key to prevent deterioration and risk of death. Since the beginning of the outbreak, the international medical organisation is also mobilising its teams to raise awareness on cholera among the different communities.